ESMO 20264Sight

28 abstracts. Madrid, October 23–27, 2026.

All ESMO 2026 highlights

Choose a tumor group

CLARITY-Gastric 01

  • 1
  • 2
  • 3
  • 4
  • 5

In brief

CLARITY-Gastric 01 (CG-01): A Phase 3 Study of Sonesitatug Vedotin (Sone-Ve) in Second or Later-Line (2L+) Advanced or Metastatic Claudin 18.2 (CLDN18.2)-Positive Gastroesophageal Carcinoma (GEC)

Phase 3 (n=532): sonesitatug vedotin (CLDN18.2-targeted ADC) vs investigator’s choice in 2L+ CLDN18.2-positive (≥25%) advanced GEC. Dual primary endpoints: OS in 3L+ and PFS in ITT.

  • 3L+ OS: 10.0 vs 5.0 mo; HR 0.47 (0.36–0.62)
  • ITT OS: 10.6 vs 6.4 mo; HR 0.58 (0.47–0.73); PFS HR 0.77, not significant
  • Grade ≥3 TRAEs 36.4% vs 44.8%
  • Significant OS benefit in 3L+ and ITT with a manageable safety profile, supporting Sone-Ve as a potential 2L+ treatment.

Rui-Hua Xu

Yelena Janjigian · Ming-Huang Chen

SAFFRON

  • 1
  • 2
  • 3
  • 4
  • 5

In brief

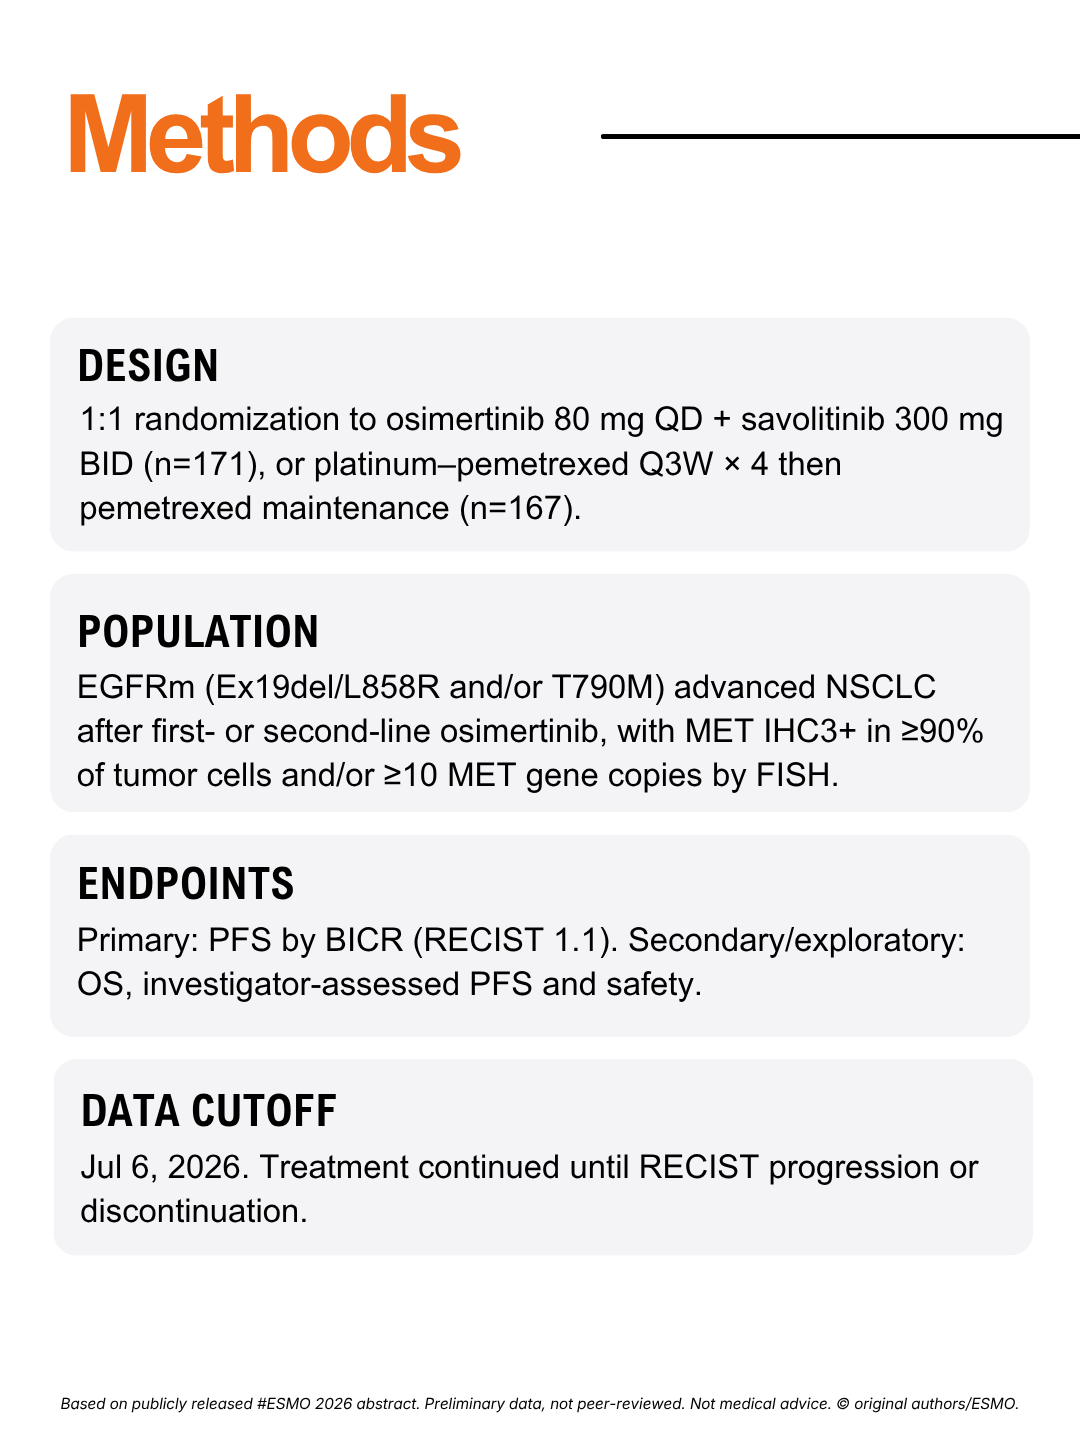
Osimertinib + Savolitinib vs Platinum–Pemetrexed in EGFRm MET-Overexpressed and/or -Amplified Advanced NSCLC Post-Osimertinib: SAFFRON Phase 3 Primary Results

Phase 3 (n=338): osimertinib + savolitinib vs platinum–pemetrexed in EGFRm, MET-overexpressed and/or amplified advanced NSCLC after osimertinib. Primary endpoint: PFS by BICR.

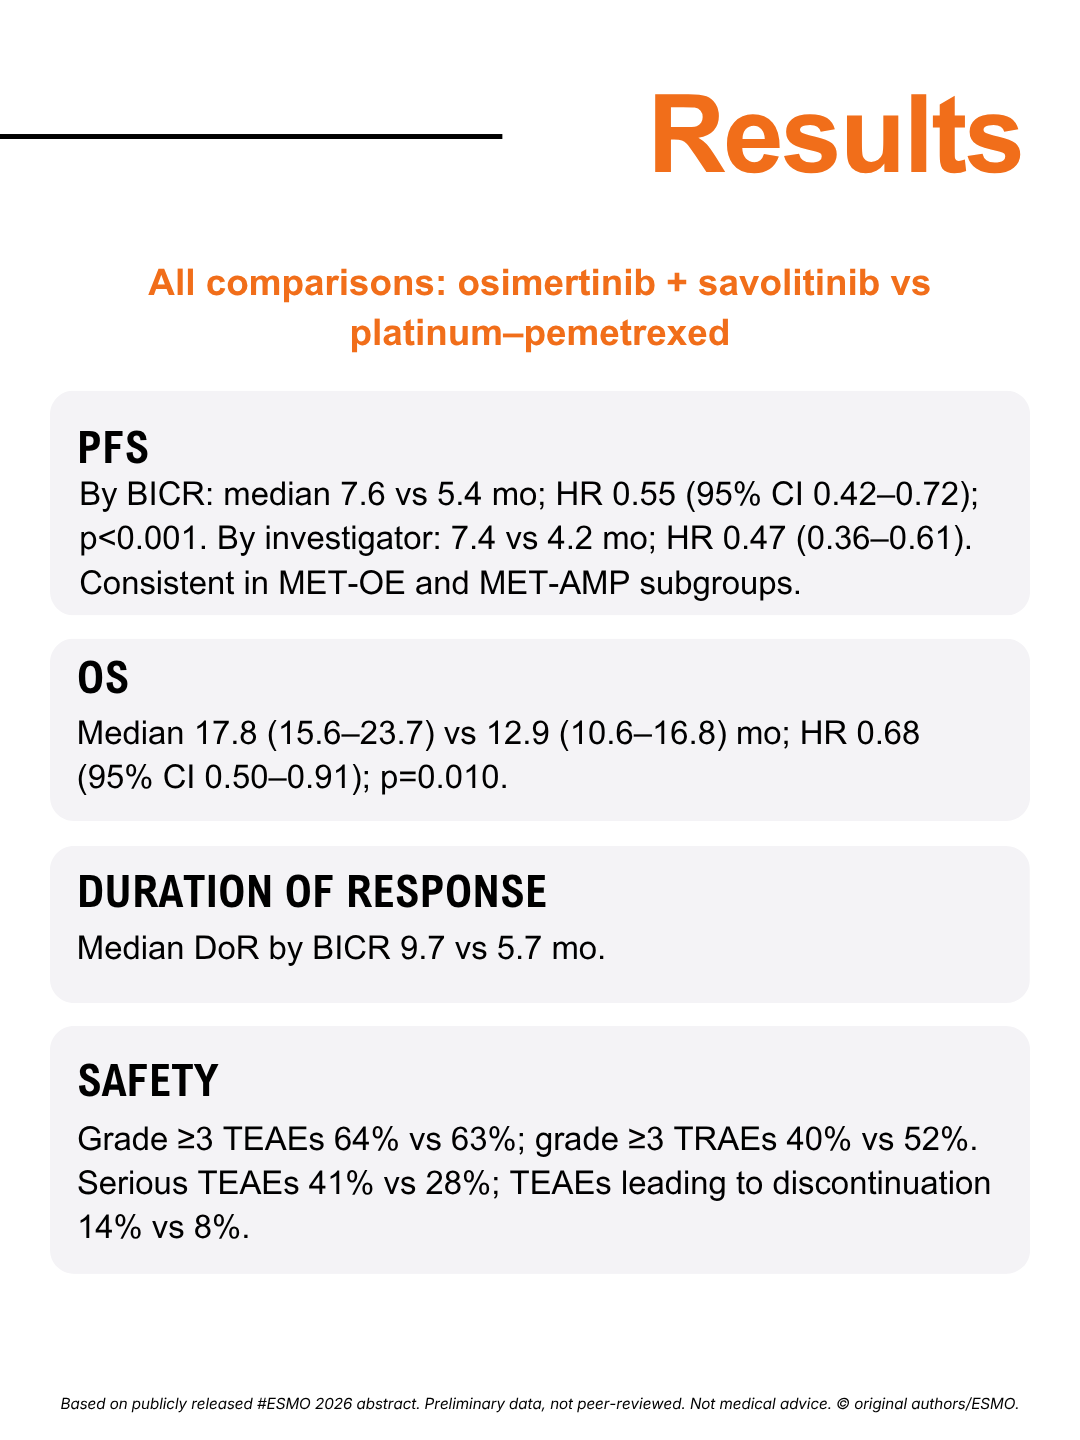
  • Median PFS 7.6 vs 5.4 mo; HR 0.55 (0.42–0.72); p<0.001
  • Median OS 17.8 vs 12.9 mo; HR 0.68 (0.50–0.91); p=0.010
  • Grade ≥3 TRAEs 40% vs 52%; serious TEAEs 41% vs 28%
  • Significant PFS and OS improvement with a manageable safety profile, establishing a new global standard of care.

Shun Lu

Nicolas Girard · Yusuke Okuma

Krascendo 1

  • `
  • 1
  • 2
  • 3
  • 4

In brief

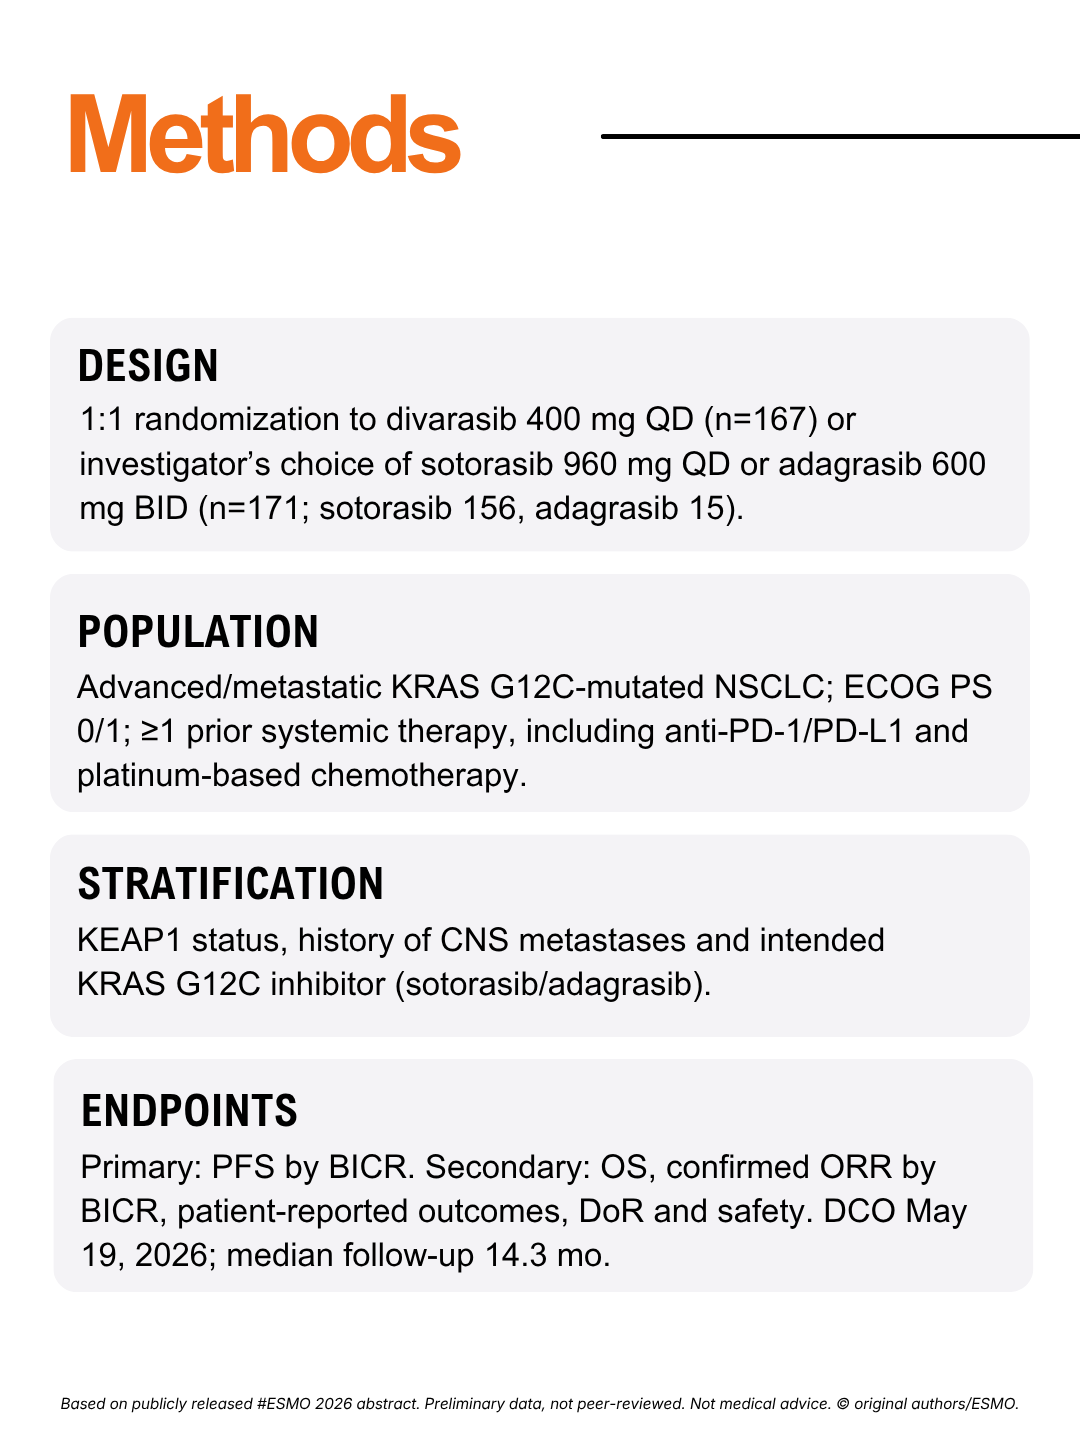
Krascendo 1: Efficacy and Safety of Divarasib vs Sotorasib or Adagrasib in Previously Treated Locally Advanced or Metastatic KRAS G12C-Mutated NSCLC

Phase 3 (n=338): divarasib vs investigator’s choice of sotorasib or adagrasib in previously treated advanced KRAS G12C-mutated NSCLC. Primary endpoint: PFS by BICR; median follow-up 14.3 mo.

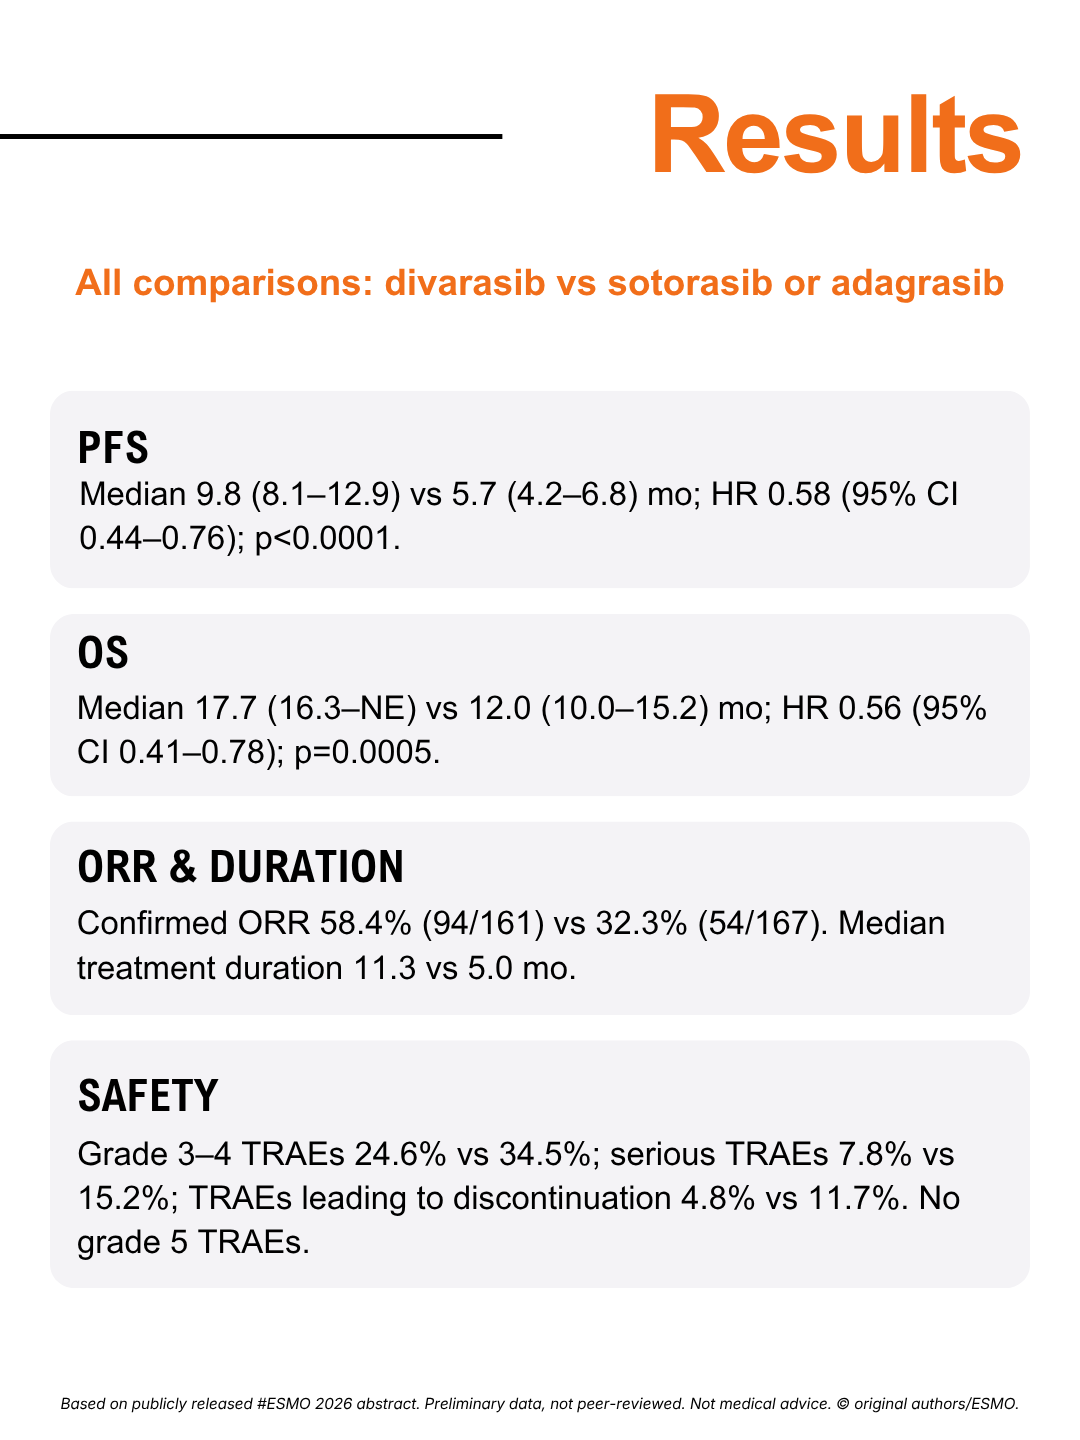
  • Median PFS 9.8 vs 5.7 mo; HR 0.58 (0.44–0.76)
  • Median OS 17.7 vs 12.0 mo; HR 0.56 (0.41–0.78)
  • ORR 58.4% vs 32.3%; grade 3–4 TRAEs 24.6% vs 34.5%
  • Significant PFS and OS improvement with a manageable safety profile, establishing divarasib as a new standard of care in this setting.

Ferdinandos Skoulidis

Myung-Ju Ahn · Shirish Gadgeel

DASL-HiCaP (ANZUP1801)

  • 1
  • 2
  • 3
  • 4
  • 5

In brief

Darolutamide With Androgen Deprivation Therapy (ADT) and Definitive or Salvage Locoregional Radiation Therapy (RT) for Localised, Very High-Risk Prostate Cancer: Interim Analysis of an International, Placebo-Controlled, Randomised Phase 3 Trial (DASL-HiCaP; ANZUP1801)

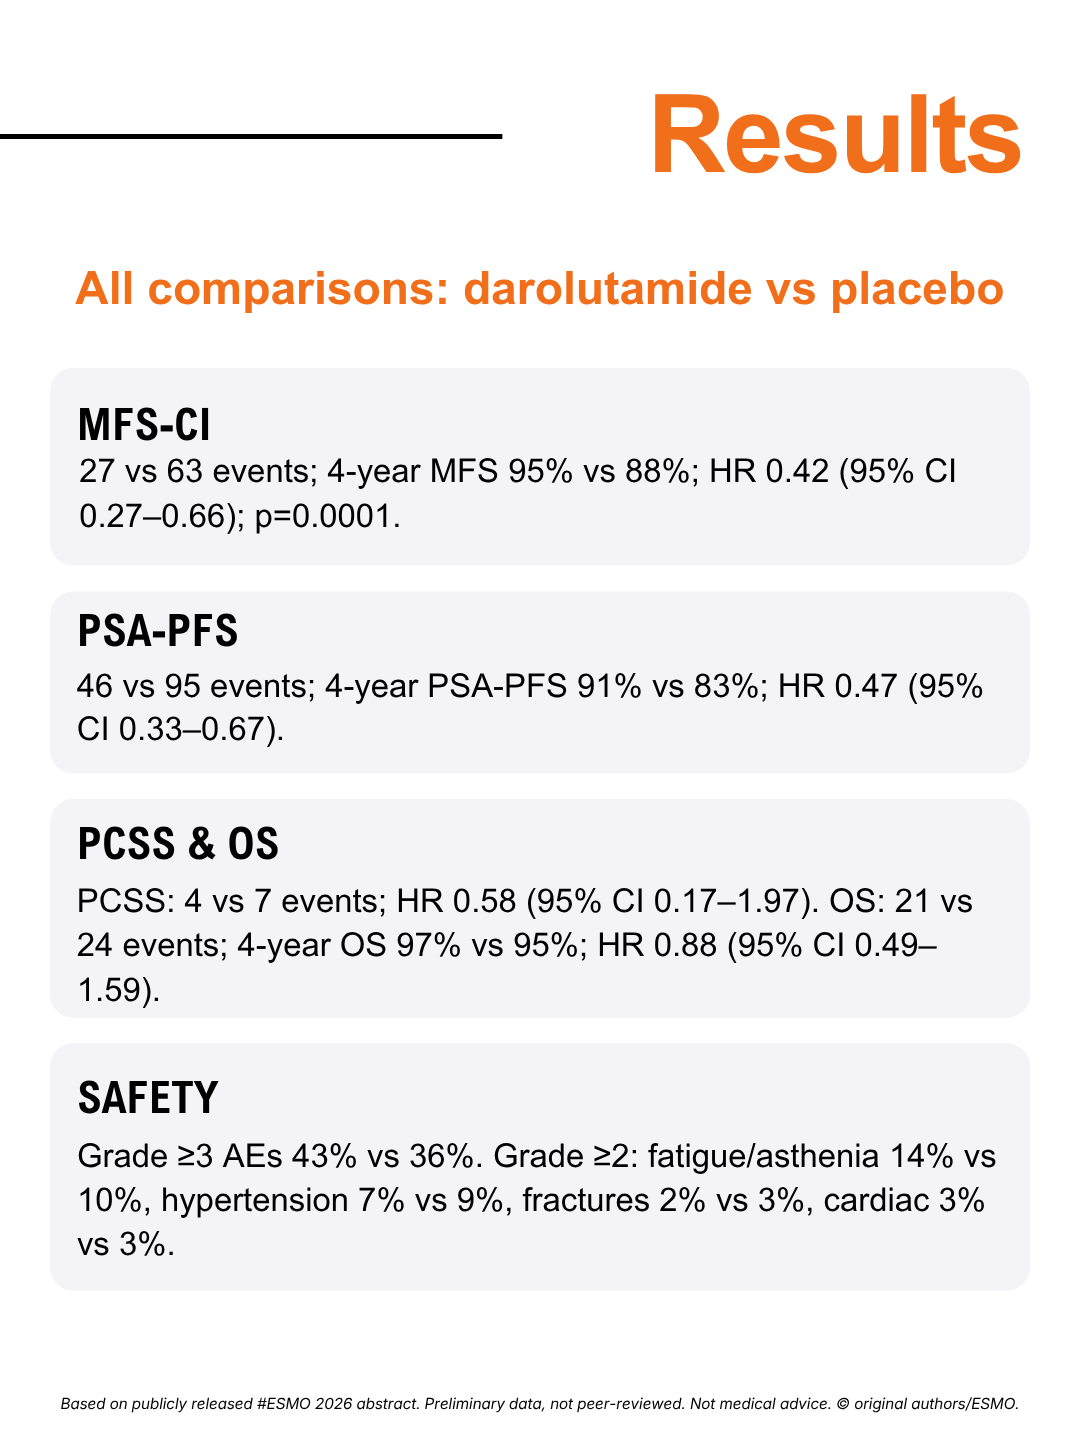
Phase 3 (n=1106): darolutamide vs placebo added to 96 weeks of ADT plus prostate/pelvic RT in very high-risk localized or post-prostatectomy persistent/recurrent prostate cancer. Interim analysis; median follow-up 3.8 years.

  • 4-yr MFS 95% vs 88%; HR 0.42 (0.27–0.66); p=0.0001
  • PSA-PFS HR 0.47 (0.33–0.67); OS HR 0.88 (0.49–1.59)
  • Grade ≥3 AEs 43% vs 36%
  • Darolutamide significantly improved MFS-CI; follow-up is ongoing to confirm MFS-CI surrogacy for OS.

Tamim Niazi
Sean McBride · Scott Williams · Ian Davis · Martin Stockler · Andrew Martin · Karen Bracken · Felicia Roncolato · Lisa Horvath · Shomik Sengupta · Jarad Martin · Tee Lim · Simon Hughes · Raymond McDermott · James Catto · Paul Kelly · Wendy Parulekar · Scott Morgan · Ricardo Rendon · Christopher Sweeney

DeLLphi-305

  • 1
  • 2
  • 3
  • 4
  • 5

In brief

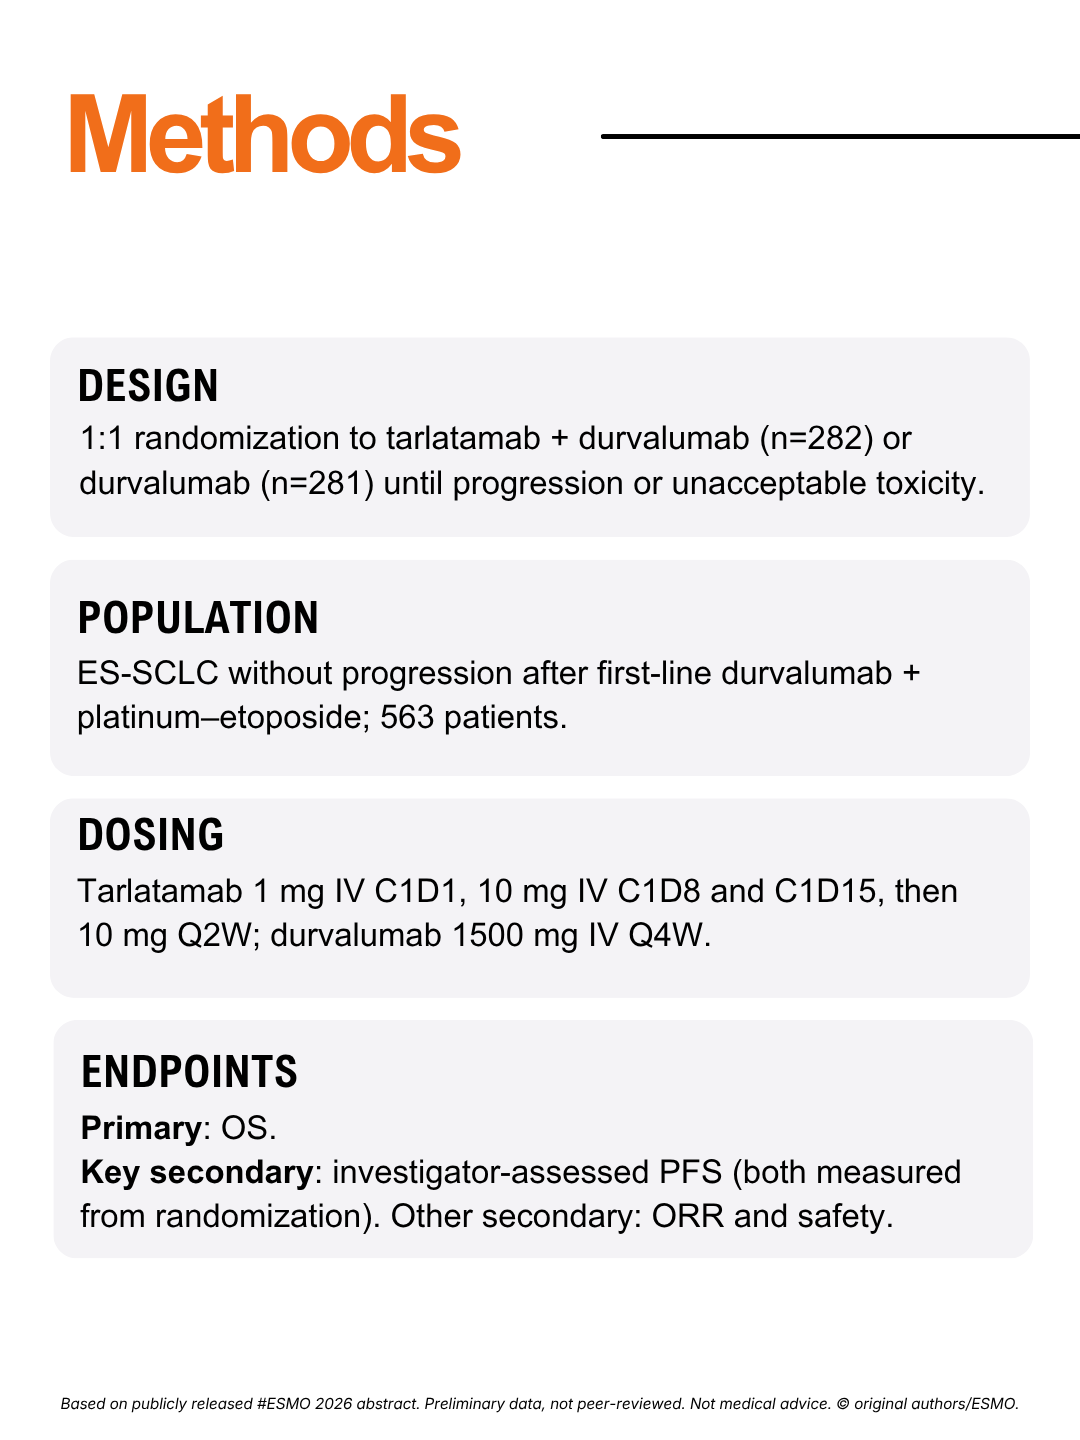
Tarlatamab Plus Durvalumab vs Durvalumab as First-Line Maintenance Therapy Following Durvalumab, Platinum, and Etoposide in Extensive-Stage Small Cell Lung Cancer (ES-SCLC): Primary Analysis of the Phase 3 DeLLphi-305 Trial

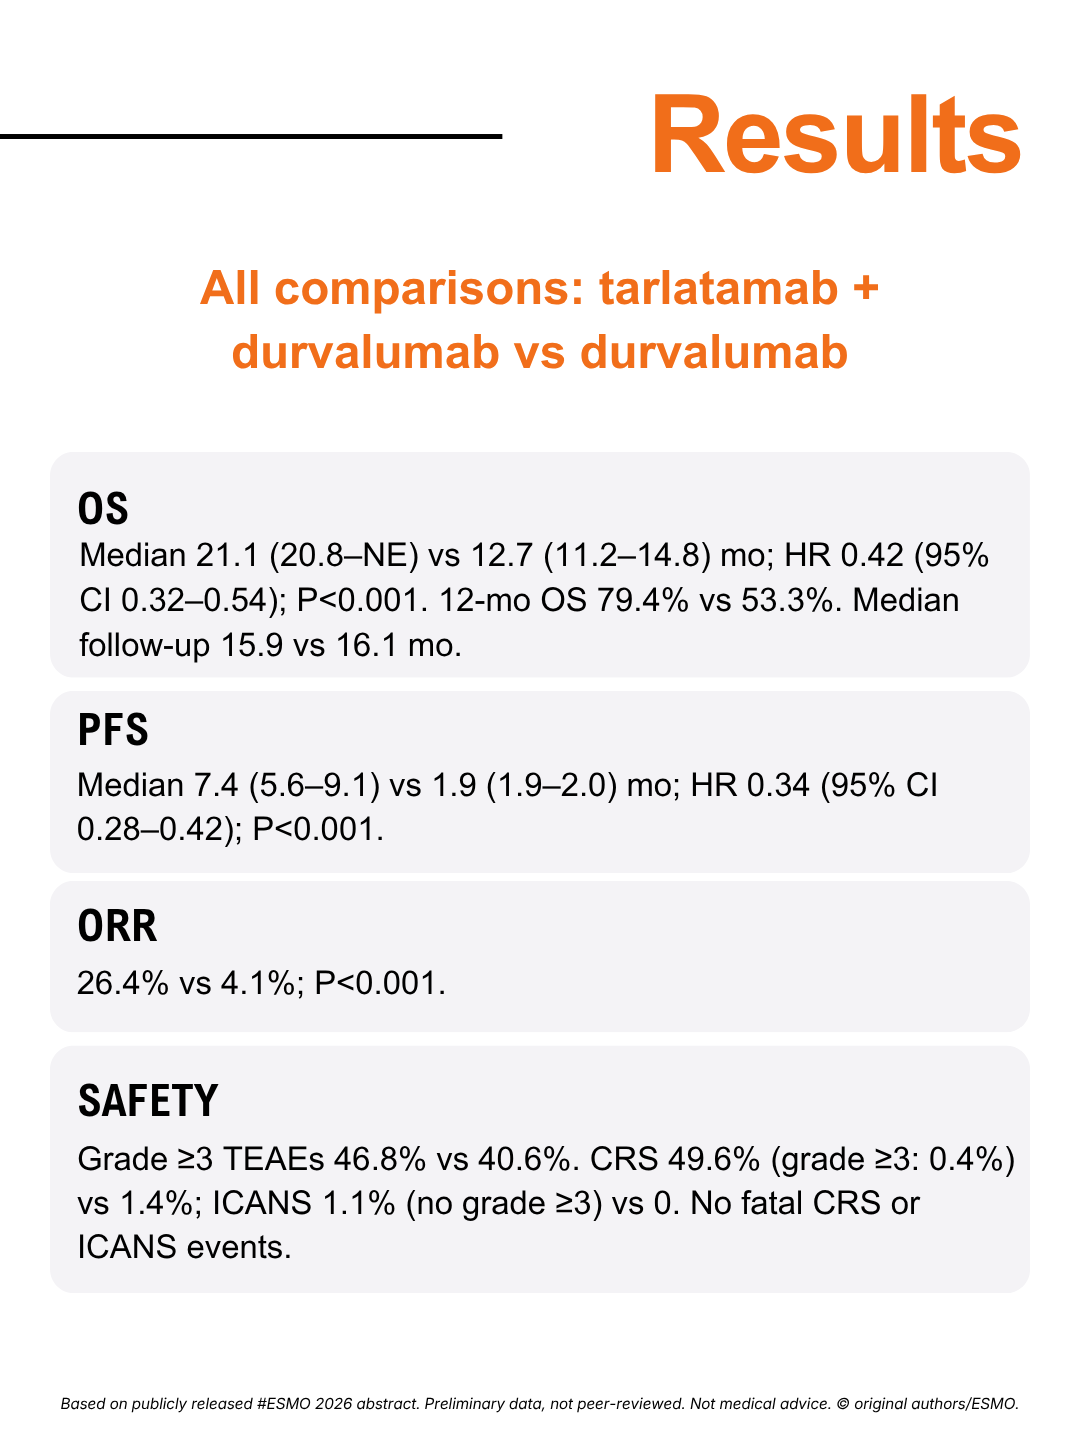
Phase 3 (n=563): tarlatamab + durvalumab vs durvalumab as first-line maintenance after durvalumab + platinum–etoposide in ES-SCLC. Primary endpoint: OS.

  • Median OS 21.1 vs 12.7 mo; HR 0.42 (0.32–0.54); P<0.001
  • Median PFS 7.4 vs 1.9 mo; HR 0.34 (0.28–0.42); ORR 26.4% vs 4.1%
  • Grade ≥3 TEAEs 46.8% vs 40.6%; CRS 49.6% (grade ≥3: 0.4%)
  • Significant OS, PFS and ORR improvement, establishing tarlatamab + durvalumab as a new standard of care first-line maintenance therapy for ES-SCLC.

Jacob Sands

Abstract LBA2

VOLGA

  • 1
  • 2
  • 3
  • 4
  • 5

In brief

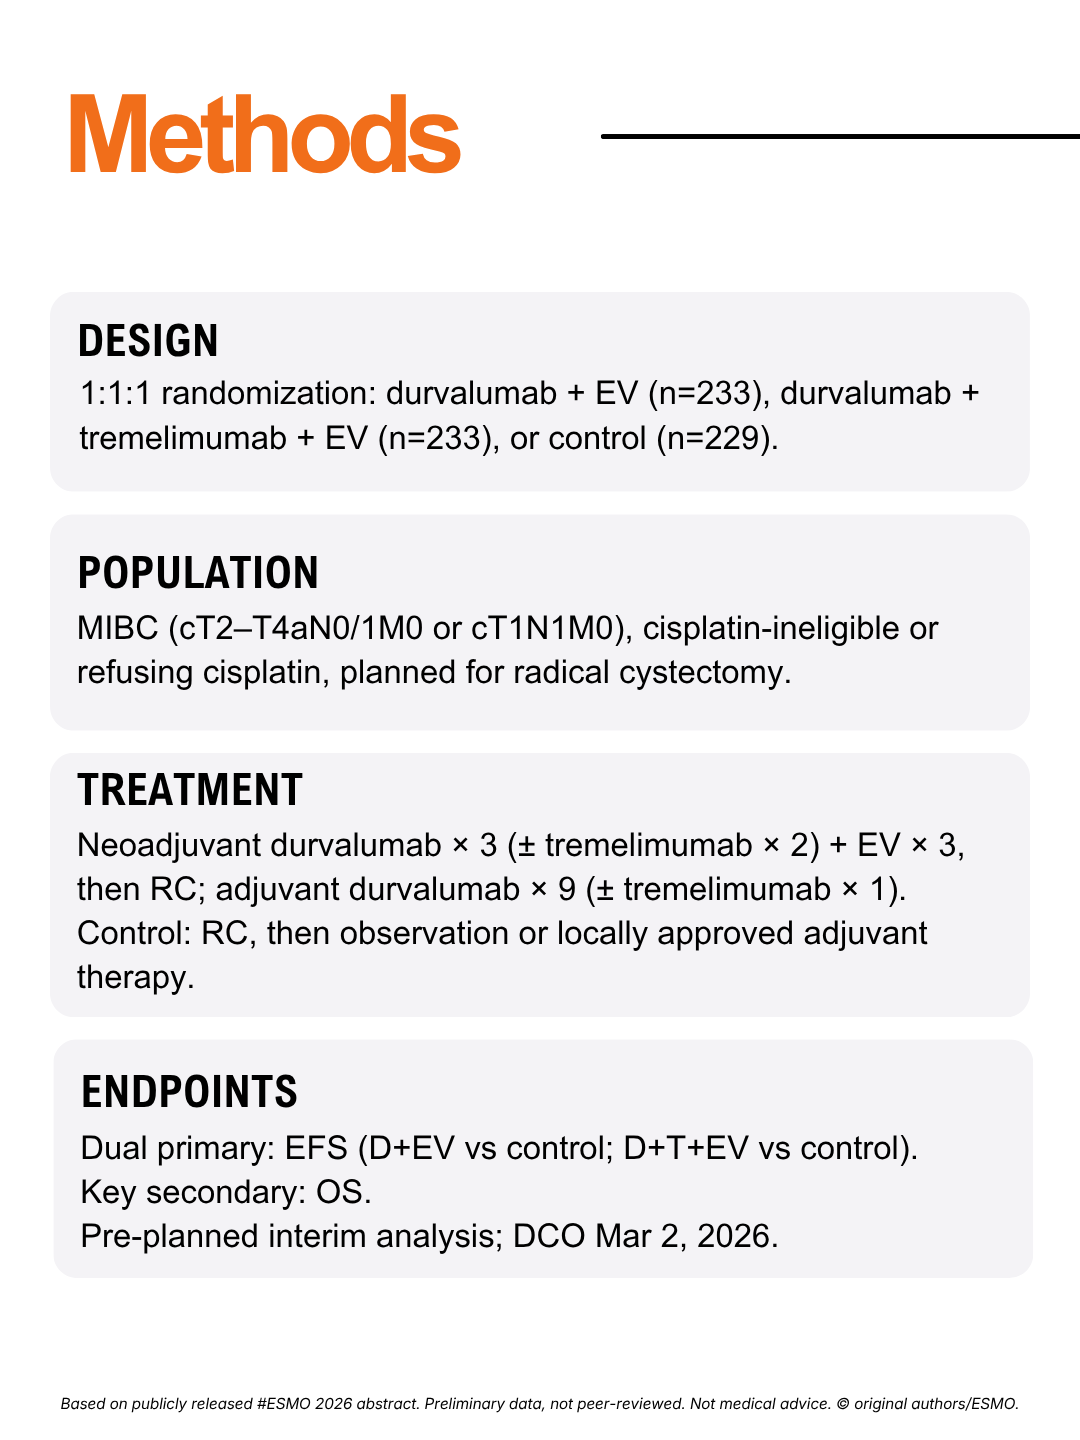
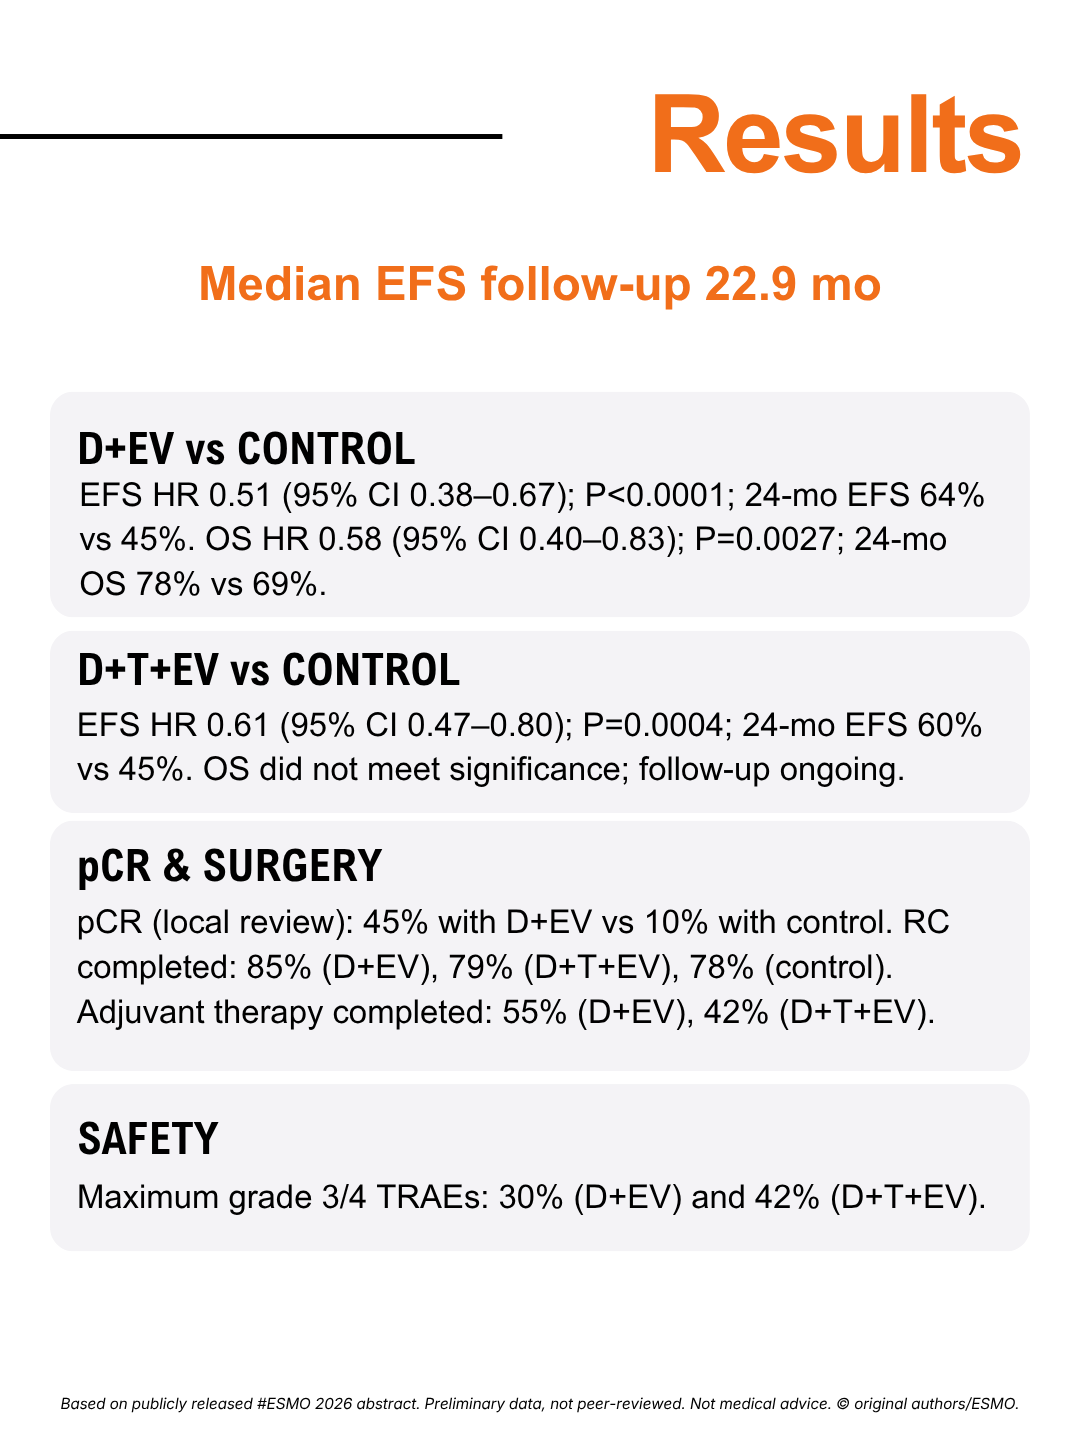
Perioperative Durvalumab With or Without Tremelimumab Plus Neoadjuvant Enfortumab Vedotin in Muscle-Invasive Bladder Cancer: Results From the Phase 3 VOLGA Trial

Phase 3 (n=695): perioperative durvalumab ± tremelimumab + neoadjuvant enfortumab vedotin vs control (RC, then observation or approved adjuvant therapy) in cisplatin-ineligible MIBC. Interim analysis; median EFS follow-up 22.9 mo.

  • D+EV: EFS HR 0.51 (0.38–0.67); OS HR 0.58 (0.40–0.83)
  • D+T+EV: EFS HR 0.61 (0.47–0.80); OS did not meet significance
  • pCR 45% (D+EV) vs 10% (control); grade 3/4 TRAEs 30% and 42%
  • Both EFS primary endpoints met; perioperative durvalumab plus 3 cycles of neoadjuvant EV also significantly improved OS.

Thomas Powles
Alexandra Drakaki · Jeremy Teoh · Enrique Grande · Mario Fontes-Sousa · Camillo Porta · Esther Wu · Erik Goluboff · Svetlana Ho · Stephan Hois · Ashok Gupta · James Catto

LBA1

  • 1
  • 2
  • 3
  • 4
  • 5

In brief

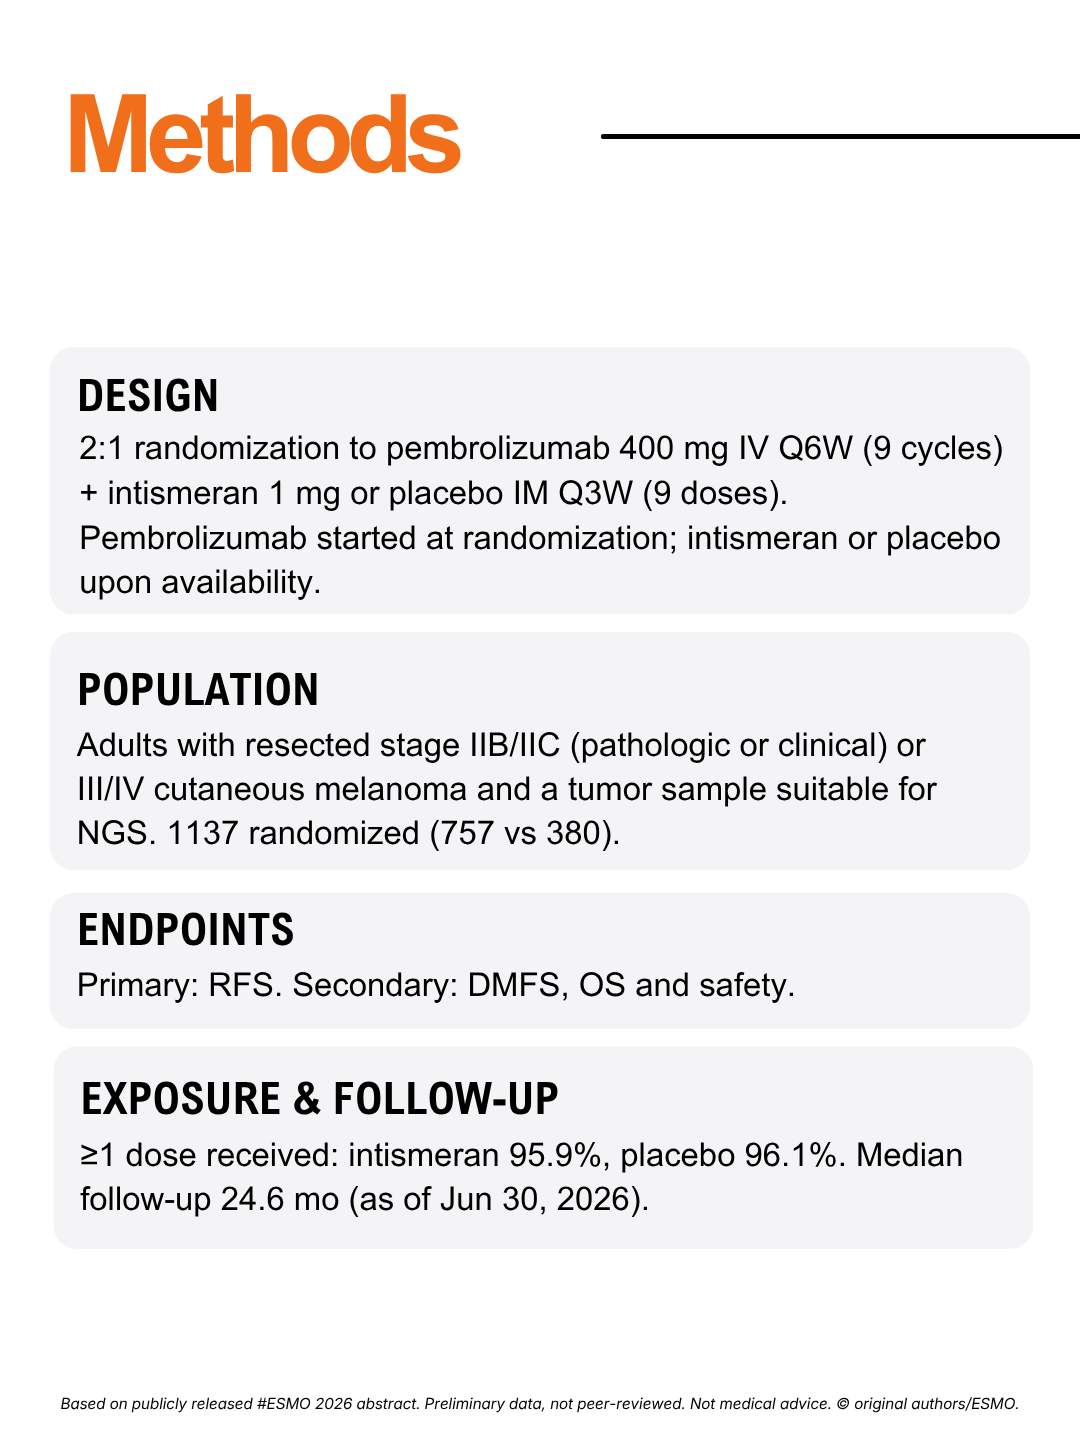
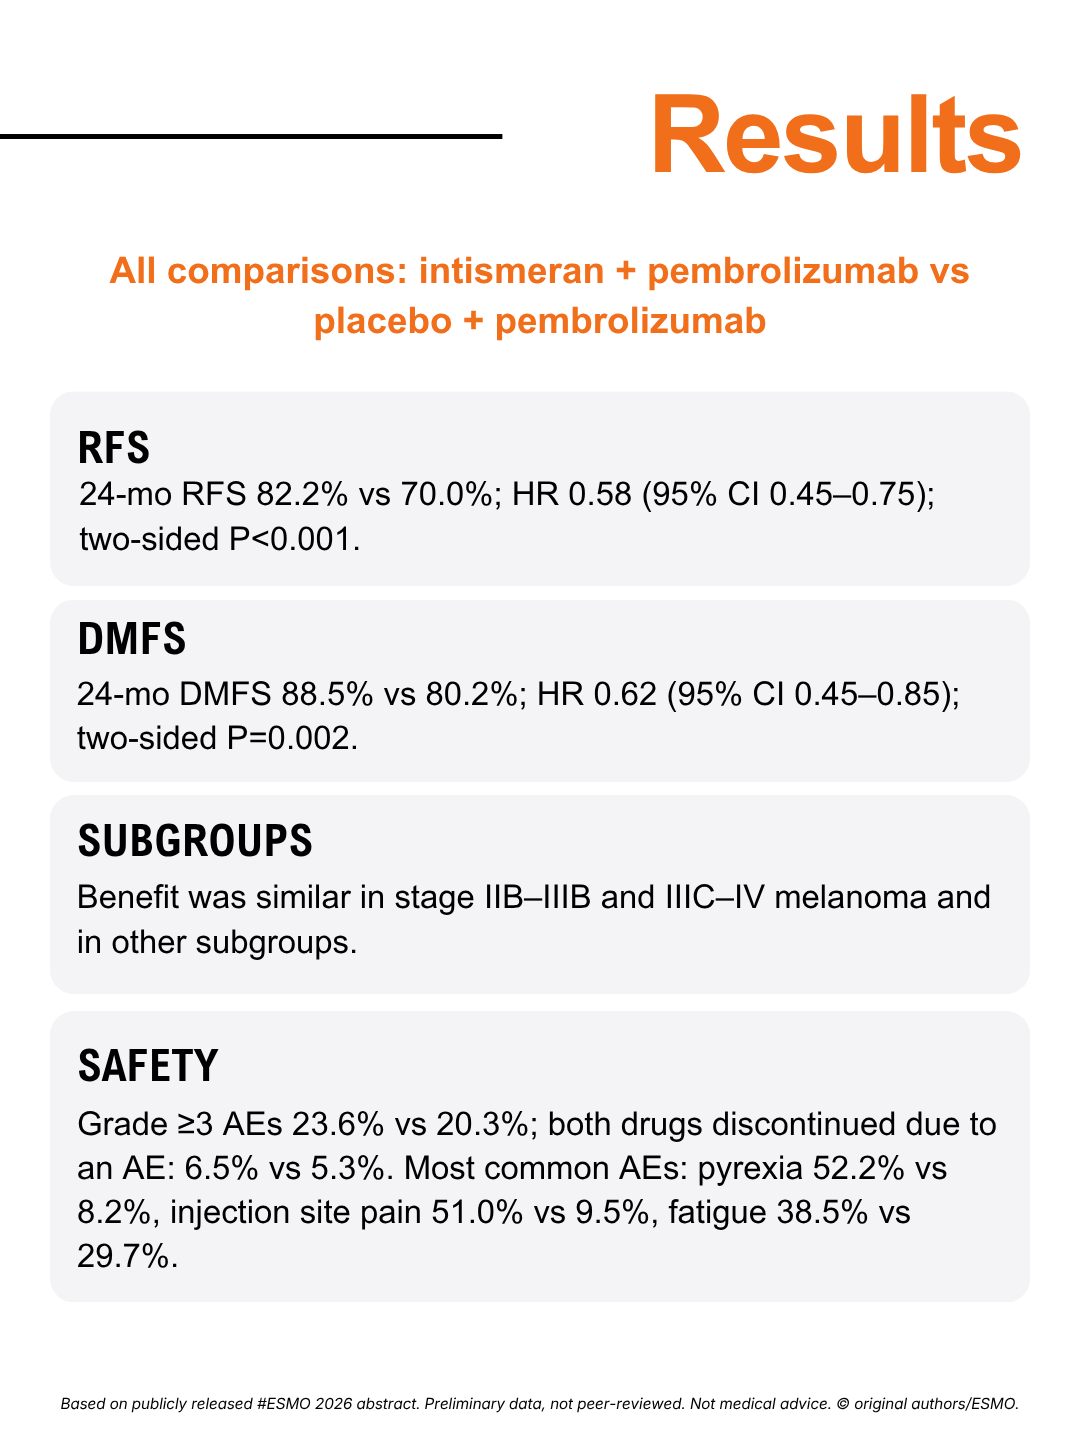
INTerpath-001: Phase 3 Study of the mRNA-Based Individualized Neoantigen Therapy Intismeran Autogene Plus Pembrolizumab vs Pembrolizumab Alone for Adjuvant Treatment of Resected Stage IIB–IV Melanoma

Double-blind phase 3 (n=1137, 2:1): mRNA individualized neoantigen therapy intismeran + pembrolizumab vs placebo + pembrolizumab, adjuvant, in resected stage IIB–IV melanoma. Median follow-up 24.6 mo.

  • 24-mo RFS 82.2% vs 70.0%; HR 0.58 (0.45–0.75); P<0.001
  • 24-mo DMFS 88.5% vs 80.2%; HR 0.62 (0.45–0.85); P=0.002
  • Grade ≥3 AEs 23.6% vs 20.3%; pyrexia 52.2% vs 8.2%
  • Significantly improved RFS and DMFS, generally well tolerated; the findings set a new benchmark for adjuvant melanoma.

Georgina Long
Jeffrey Weber · Jason Luke · Matteo Carlino · Adnan Khattak · Robert Meehan · Michelle Brown · Jinchun Zhang · Clemens Krepler · Paul Duic

FLAURA2

  • 1
  • 2
  • 3
  • 4
  • 5

In brief

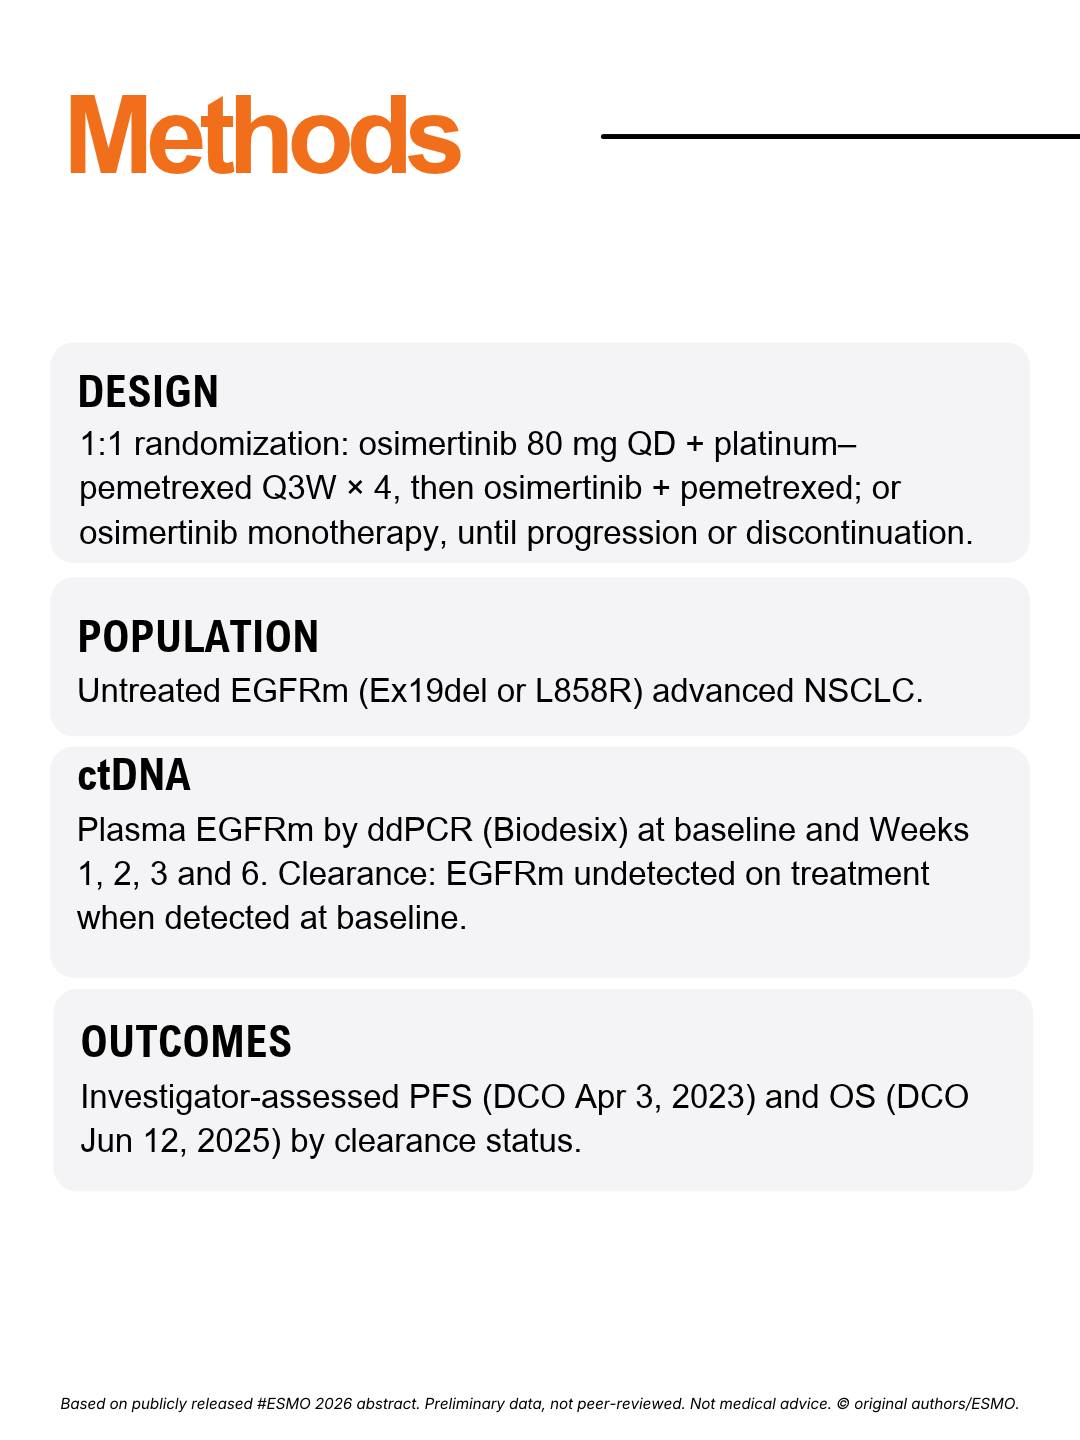
FLAURA2: Analysis of On-Treatment Plasma EGFRm Dynamics and Associated Clinical Outcomes in Patients With EGFRm Advanced NSCLC Treated With First-Line Osimertinib ± Platinum–Pemetrexed

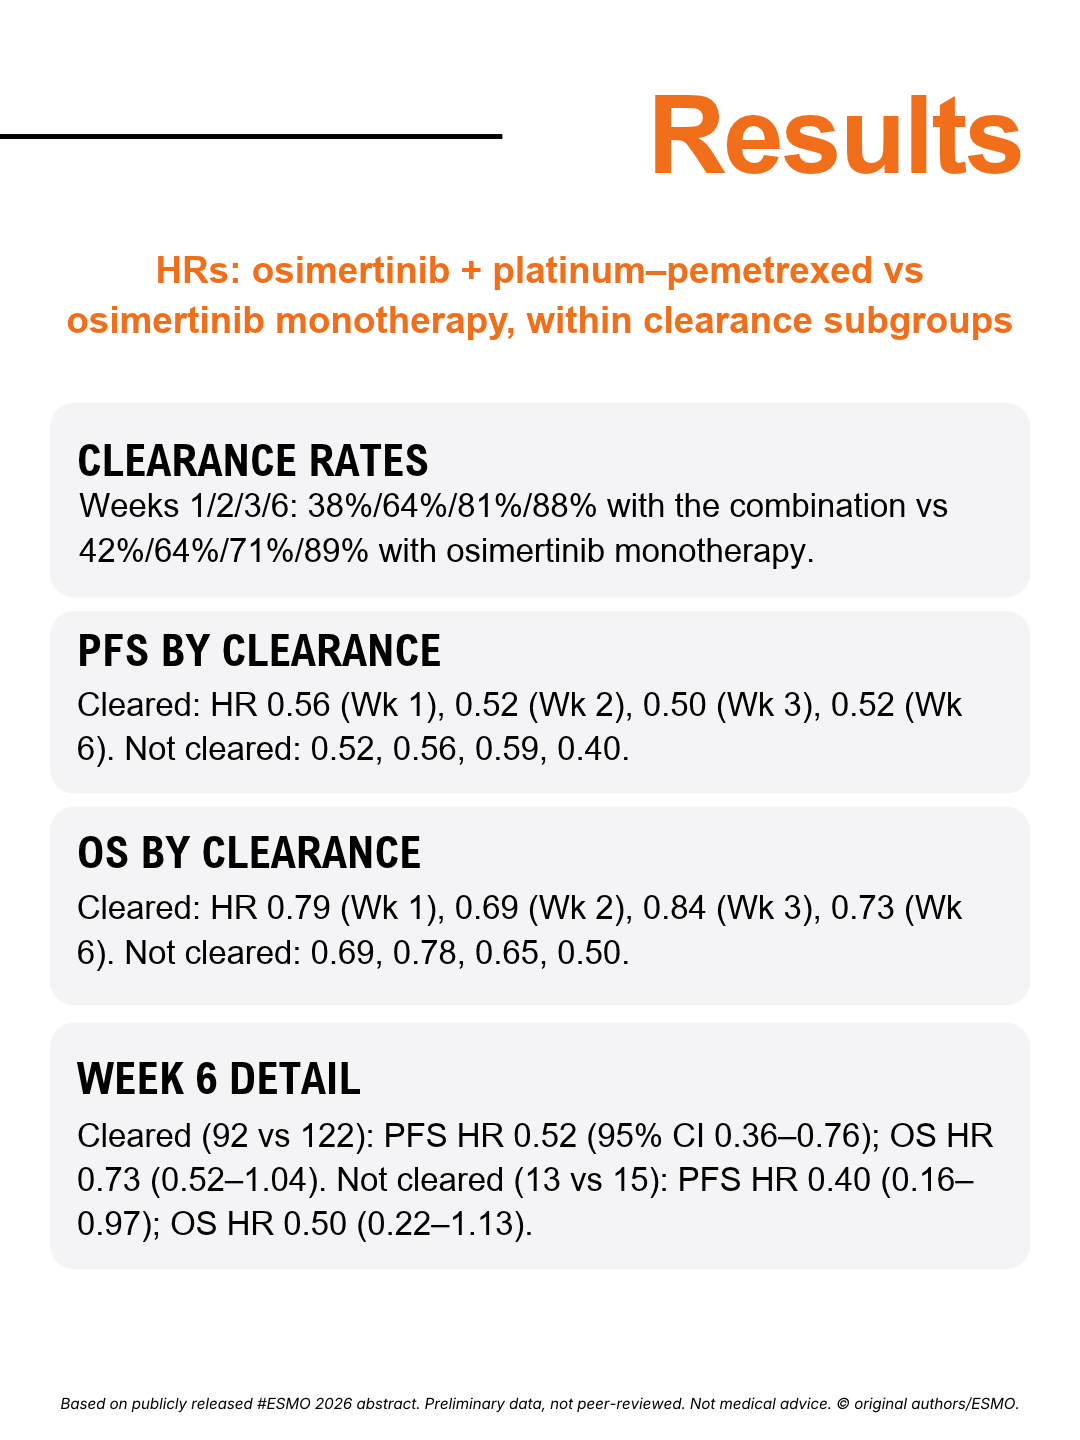
Exploratory ctDNA analysis of phase III FLAURA2: plasma EGFRm clearance (ddPCR) at Weeks 1, 2, 3 and 6 with first-line osimertinib ± platinum–pemetrexed in EGFRm advanced NSCLC.

  • Week 6 clearance: 88% vs 89%
  • Week 6 cleared: PFS HR 0.52 (0.36–0.76); not cleared: PFS HR 0.40 (0.16–0.97)
  • Week 6 OS HR 0.73 (cleared) and 0.50 (not cleared)
  • Clearance was prognostic but not predictive; osimertinib + platinum–pemetrexed was superior to osimertinib regardless of clearance status.

David Planchard

Pasi Jänne · Ying Cheng · James Yang · Noriko Yanagitani · Sang-We Kim · Shunichi Sugawara · Yan Yu · Yun Fan · Sarayut Geater · Konstantin Laktionov · Chee Lee · Natalia Valdiviezo · Samreen Ahmed · Jean-Marc Maurel · Igor Andrasina · Jonathan Goldman · Dana Ghiorghiu · Yuri Rukazenkov · Alex Todd · Kunihiko Kobayashi

459O

  • 1
  • 2
  • 3
  • 4
  • 5

In brief

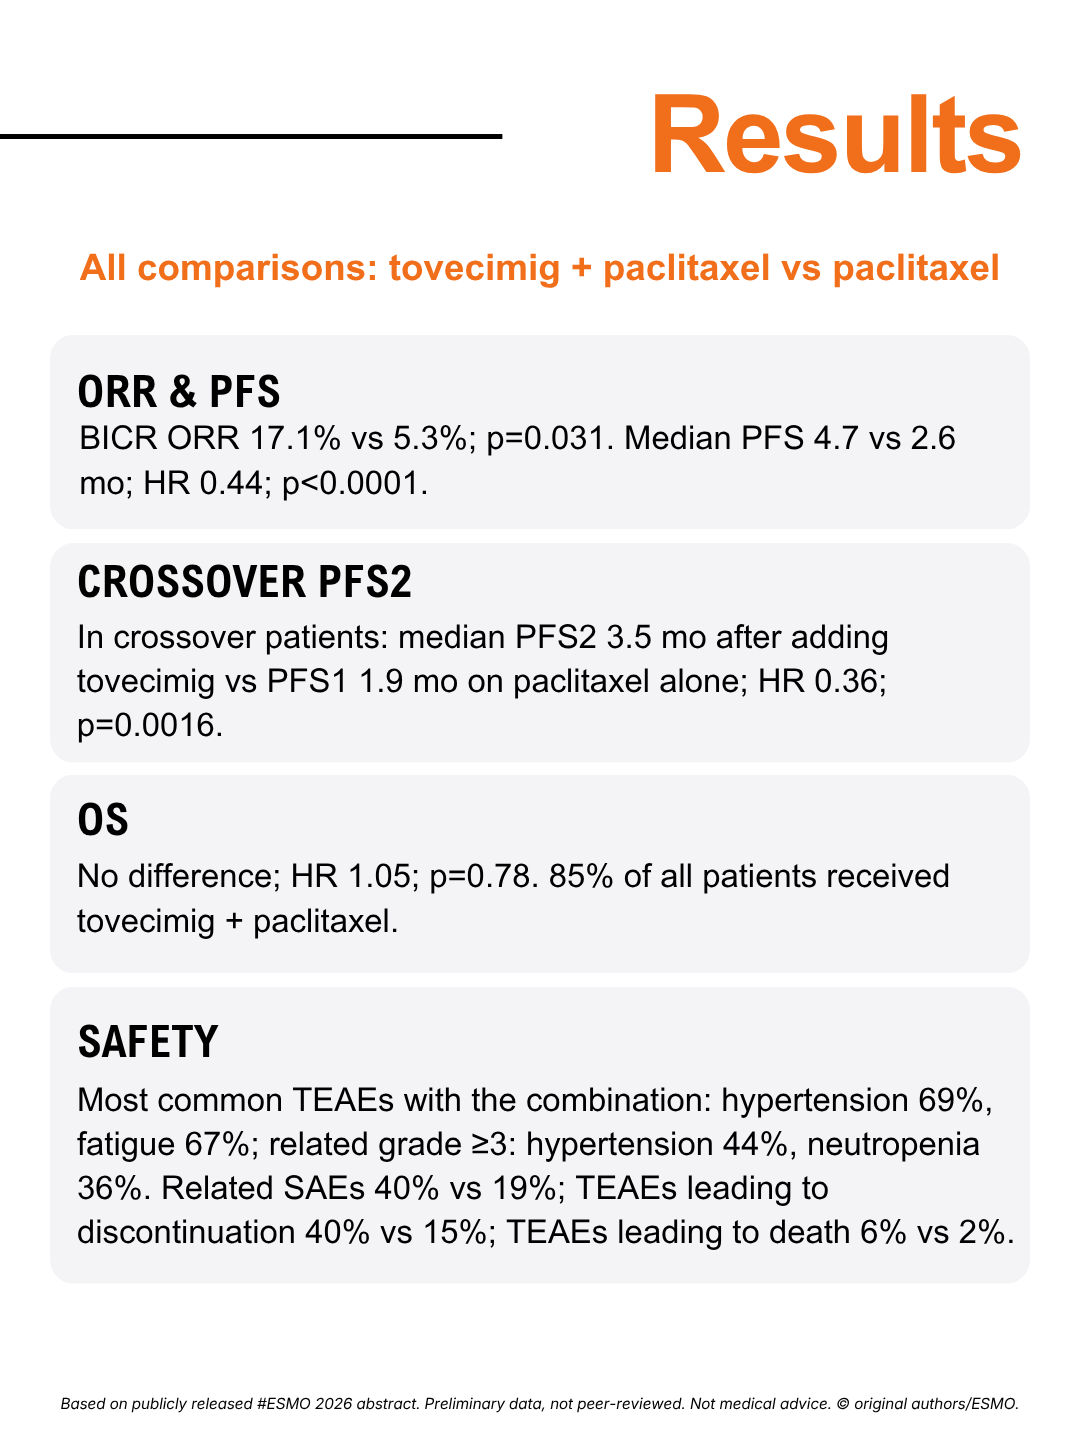
A Randomized Trial of Paclitaxel ± Tovecimig in Previously Treated Patients With Advanced Biliary Tract Cancer

Randomized phase 2/3 (n=168, 2:1): tovecimig (DLL4 × VEGF-A bispecific) + paclitaxel vs paclitaxel in previously treated advanced BTC. Primary endpoint: BICR ORR.

ORR 17.1% vs 5.3% (p=0.031); median PFS 4.7 vs 2.6 mo, HR 0.44 (p<0.0001)
OS HR 1.05 (p=0.78); 54% crossed over to tovecimig + paclitaxel
Related grade ≥3 hypertension 44%; TEAEs leading to discontinuation 40% vs 15%
Significant ORR and PFS advantage; OS analysis confounded by high crossover, precluding a meaningful comparison.

Nilofer Azad

Zishuo Hu · Ilyas Sahin · Renuka Iyer · Olivia Aranha · Howard Hochster · Priyadarshini Pathak · Scott Paulson · Aparna Kalyan · Chih-Yi Liao · Nguyen Tran · Robin Kelley · Gregory Heestand · David Cosgrove · Anthony El-Khoueiry · Mitesh Borad · Nashat Gabrail · Umair Majeed · Lingling Du · Suneel Kamath · Nathan Shumway · Rachna Shroff · Lipika Goyal · Minori Rosales · Milind Javle

4736O

  • 1
  • 2
  • 3
  • 4
  • 5

In brief

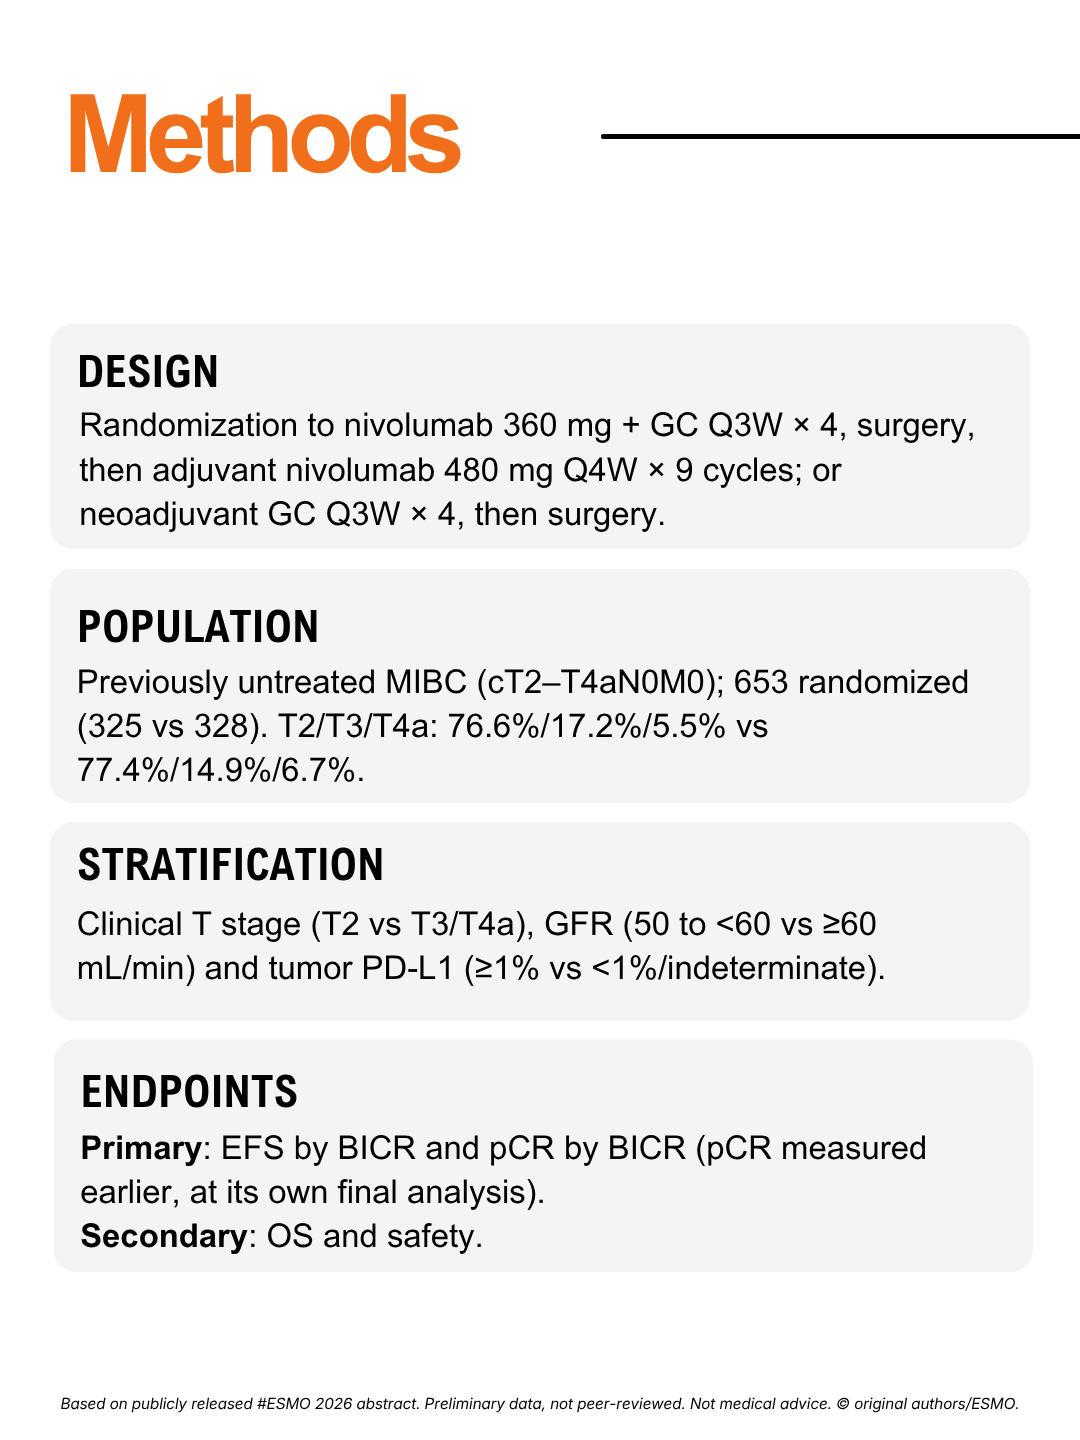
Results From a Phase 3 Trial of Neoadjuvant Chemotherapy Alone vs in Combination With Nivolumab Followed by Postsurgical Adjuvant Nivolumab in Patients With Muscle-Invasive Bladder Cancer (MIBC)

Phase 3 (n=653): neoadjuvant nivolumab + gemcitabine/cisplatin then adjuvant nivolumab vs neoadjuvant GC in MIBC. Primary endpoints: EFS and pCR.

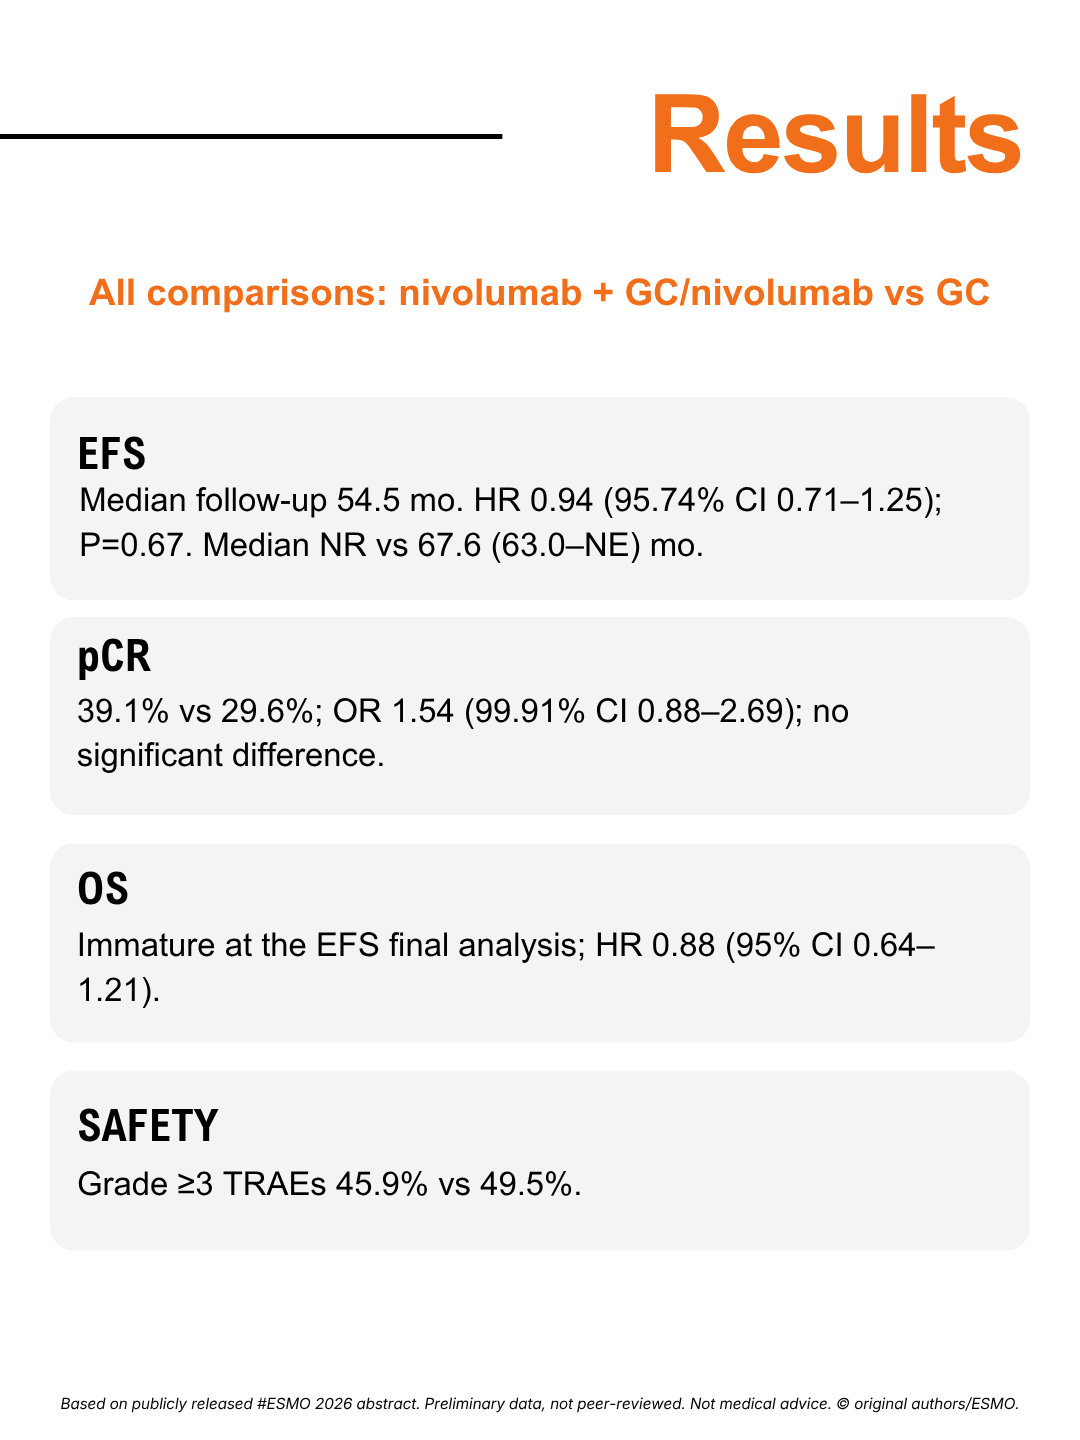
EFS HR 0.94 (95.74% CI 0.71–1.25); P=0.67
pCR 39.1% vs 29.6%; OR 1.54 (99.91% CI 0.88–2.69)
OS immature: HR 0.88 (0.64–1.21); grade ≥3 TRAEs 45.9% vs 49.5%
No statistically significant differences in EFS or pCR; safety of nivolumab + GC consistent with the individual agents.

Andrea Necchi

4449RO

  • 1
  • 2
  • 3
  • 4
  • 5

In brief

Paired-Biopsy Multi-Omic Analysis Reveals Target-Independent Mechanisms of Antibody–Drug Conjugate (ADC) Resistance in Metastatic Breast Cancer (MBC)

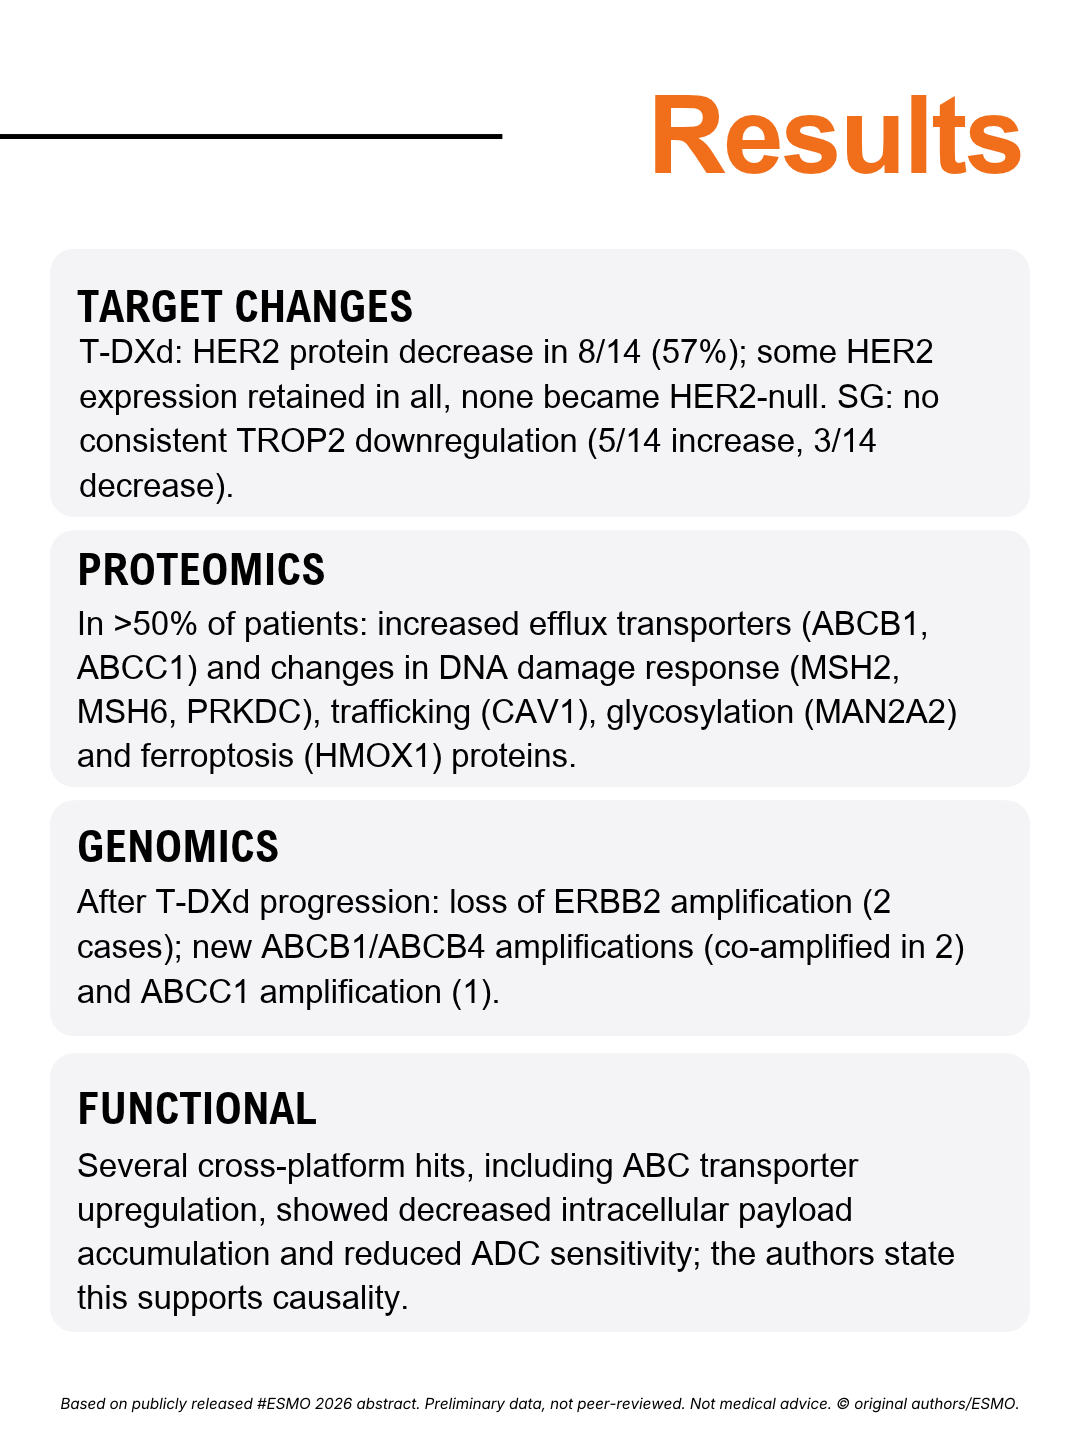
Paired-biopsy multi-omic study (n=26): pre-treatment vs post-progression MBC biopsies after T-DXd, sacituzumab govitecan, or both.

T-DXd: HER2 decreased in 57%, but none became HER2-null
SG: no consistent TROP2 downregulation (5/14 up, 3/14 down)
>50% had increased efflux transporters (ABCB1, ABCC1); functional validation showed reduced payload accumulation and ADC sensitivity
ADC resistance appears driven by complex adaptations beyond target modulation, highlighting drug efflux, trafficking and cellular stress responses.
Paolo Tarantino

PEARLS/KEYNOTE-091

  • 1
  • 2
  • 3
  • 4
  • 5

In brief
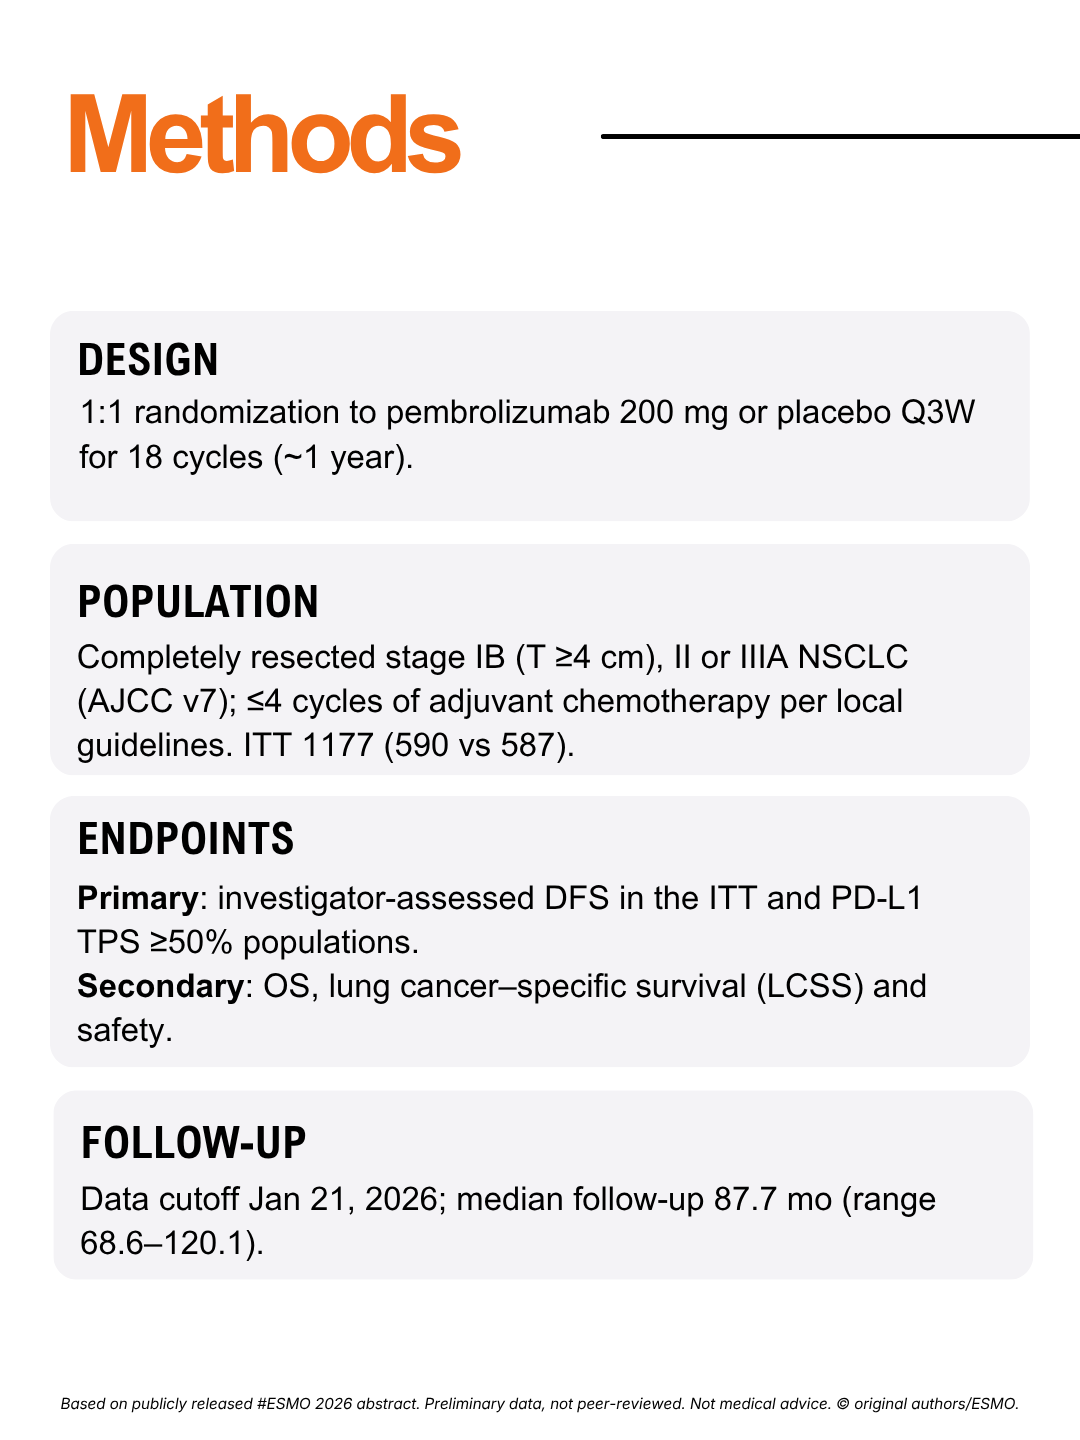
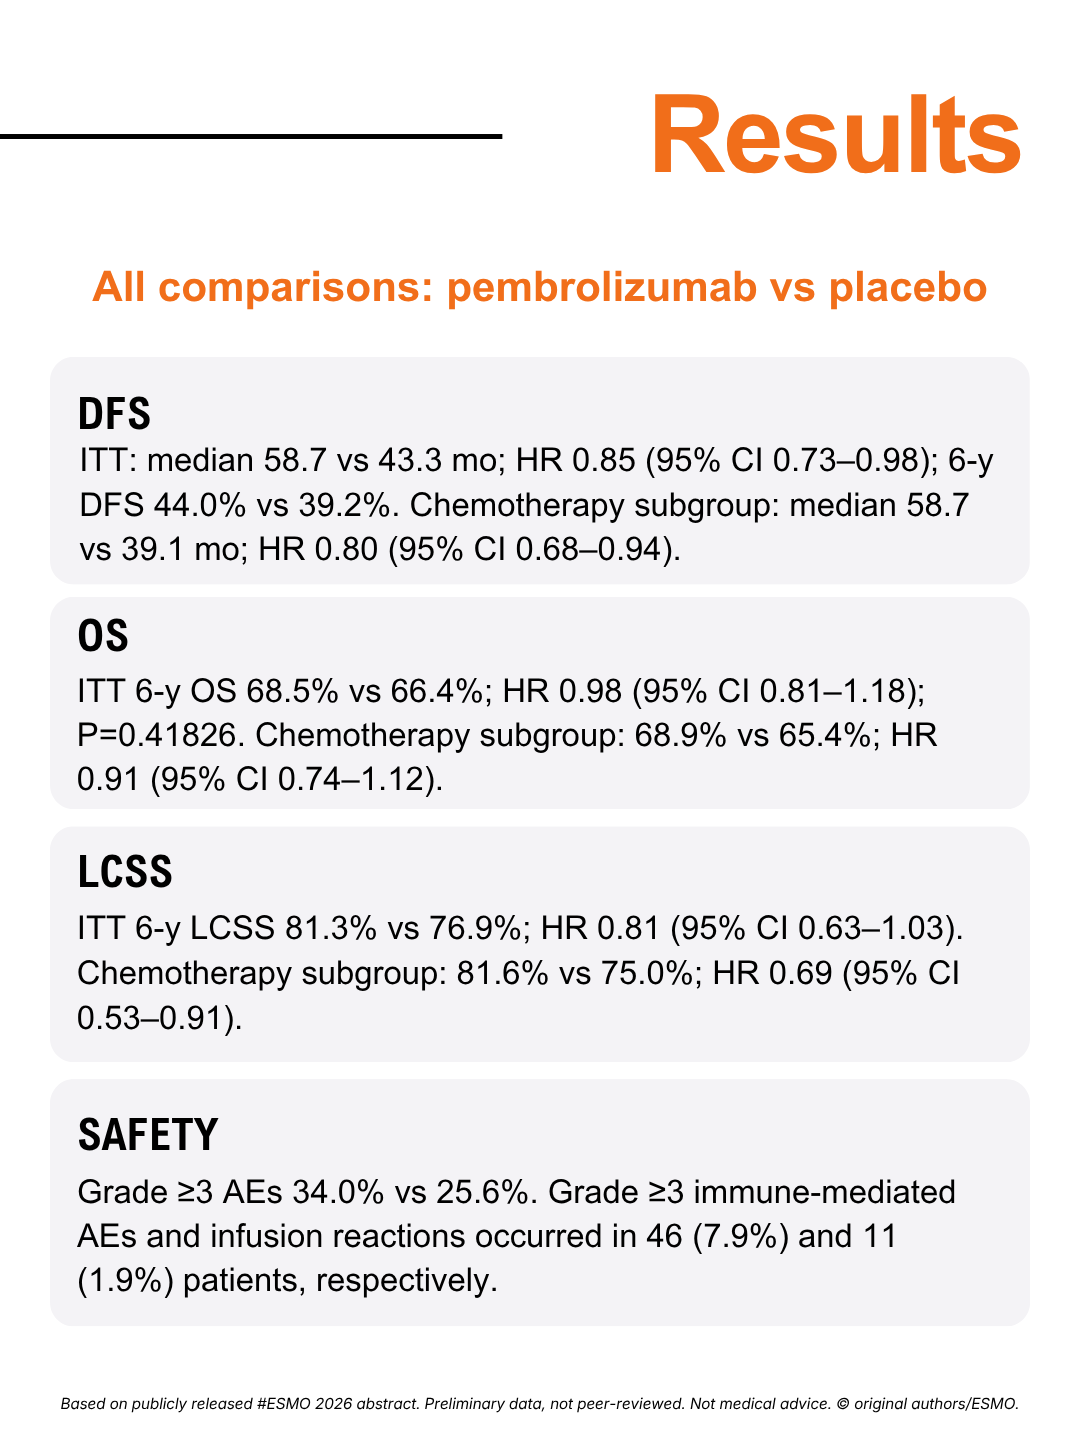
Final Analysis of Adjuvant Pembrolizumab in Resected Early-Stage Non–Small-Cell Lung Cancer (NSCLC): Phase 3 PEARLS/KEYNOTE-091 Study

Phase 3 (n=1177): adjuvant pembrolizumab vs placebo in resected stage IB–IIIA NSCLC. Final analysis; median follow-up 87.7 mo.

DFS HR 0.85 (0.73–0.98); median 58.7 vs 43.3 mo
OS HR 0.98 (0.81–1.18); 6-y OS 68.5% vs 66.4%
LCSS HR 0.81 (0.63–1.03); grade ≥3 AEs 34.0% vs 25.6%
Consistent DFS benefit with a favorable trend in LCSS and manageable safety; OS was not significantly improved, and the study was not powered for OS.

Mary O’Brien

Luis Paz-Ares · Sandrine Marreaud · Urania Dafni · Kersti Oselin · Libor Havel · Emilio Esteban · Dolores Isla · Alex Martinez-Marti · Martin Faehling · Masahiro Tsuboi · Jong-Seok Lee · Kazuhiko Nakagawa · Jing Yang · Ayman Samkari · Steven Keller · Murielle Mauer · Nitish Jha · Rolf Stahel · Benjamin Besse · Solange Peters

RAMIRIS

  • 1
  • 2
  • 3
  • 4
  • 5

In brief

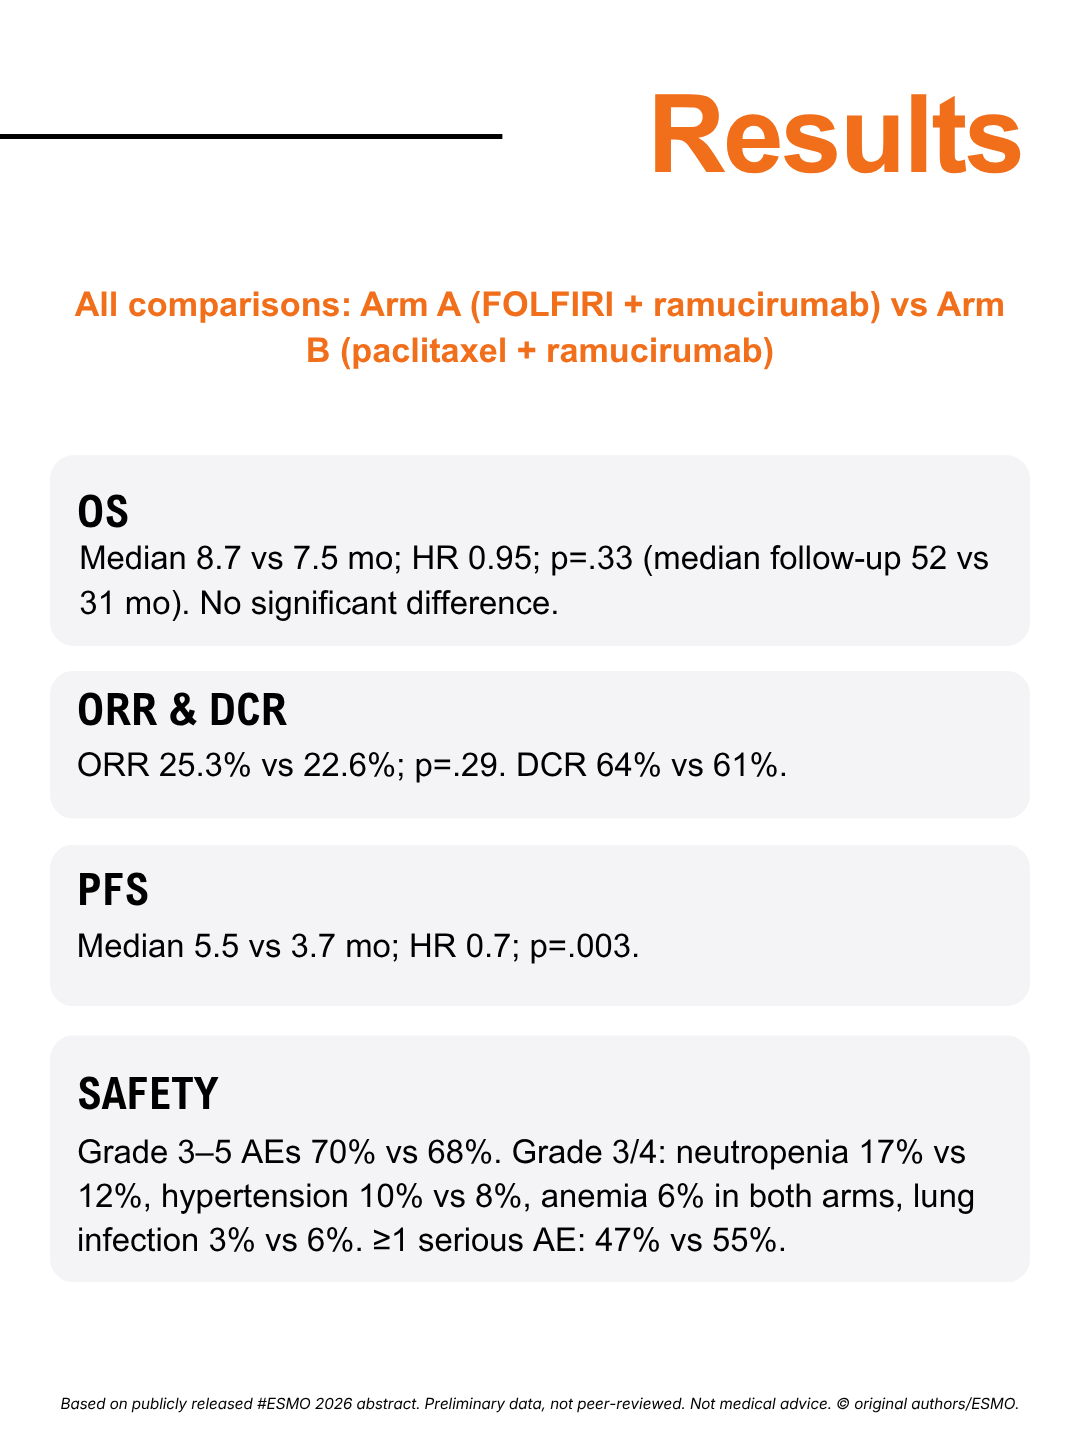
FOLFIRI Plus Ramucirumab Versus Paclitaxel Plus Ramucirumab as Second-Line Therapy for Taxane-Pretreated Patients With Advanced or Metastatic Gastroesophageal

Adenocarcinoma: Final Results of the Phase III IKFs602/AIO RAMIRIS Study

Phase III (n=317): FOLFIRI + ramucirumab vs paclitaxel + ramucirumab, second-line, in taxane-pretreated advanced GEA. Co-primary endpoints: OS and ORR.
Median OS 8.7 vs 7.5 mo; HR 0.95; p=.33
ORR 25.3% vs 22.6% (p=.29); median PFS 5.5 vs 3.7 mo, HR 0.7 (p=.003)
Grade 3–5 AEs 70% vs 68%
Co-primary endpoints were not met; PFS was clearly improved, supporting personalized treatment decisions in taxane-pretreated advanced GEA.

Magdalena Scheck

KEYNOTE-564

  • 1
  • 2
  • 3
  • 4
  • 5

In brief

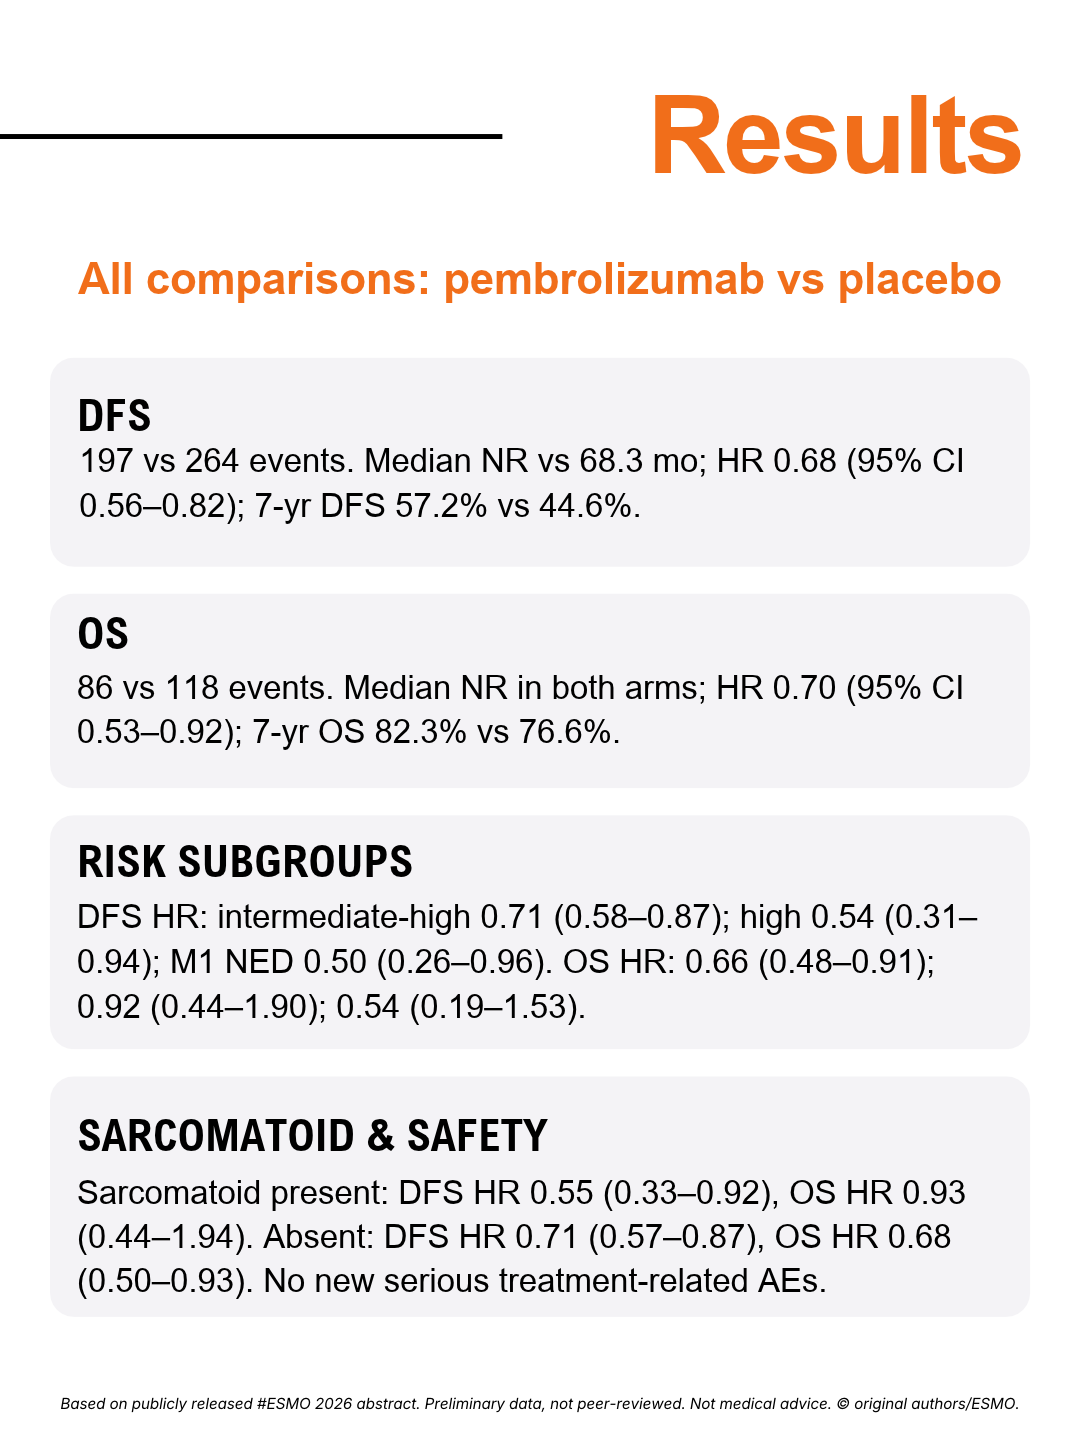
Final Protocol-Prespecified Analysis of the Phase 3 KEYNOTE-564 Trial of Adjuvant Pembrolizumab Versus Placebo in Clear Cell Renal Cell Carcinoma (ccRCC)

Phase 3 (n=994): adjuvant pembrolizumab vs placebo after nephrectomy in ccRCC at high risk of recurrence. Final prespecified analysis; median follow-up 85.9 mo.

DFS HR 0.68 (0.56–0.82); 7-yr DFS 57.2% vs 44.6%
OS HR 0.70 (0.53–0.92); 7-yr OS 82.3% vs 76.6%
No new serious treatment-related AEs
DFS and OS benefits remained consistent with earlier reports, supporting adjuvant pembrolizumab as standard treatment for ccRCC at increased risk of recurrence.

Toni Choueiri

Naomi Haas · Thomas Powles · Piotr Tomczak · Se Hoon Park · Balaji Venugopal · Stefan Symeonides · Thomas Ferguson · Yen-Hwa Chang · Jae-Lyun Lee · Piotr Sawrycki · Naveed Sarwar · Howard Gurney · Marine Gross-Goupil · John Burke · Gurjyot Doshi · Jerry Cornell · Joseph Burgents · Rodolfo Perini

evERA

  • 1
  • 2
  • 3
  • 4
  • 5

In brief

OncoAlert 4Sight, #ESMO2026

Retrospective Exploratory Biomarker Analyses From evERA Breast Cancer: A Phase III Trial of Giredestrant + Everolimus in Patients With Oestrogen Receptor-Positive, HER2-Negative Advanced Breast Cancer in the Post-CDK4/6 Inhibitor Setting

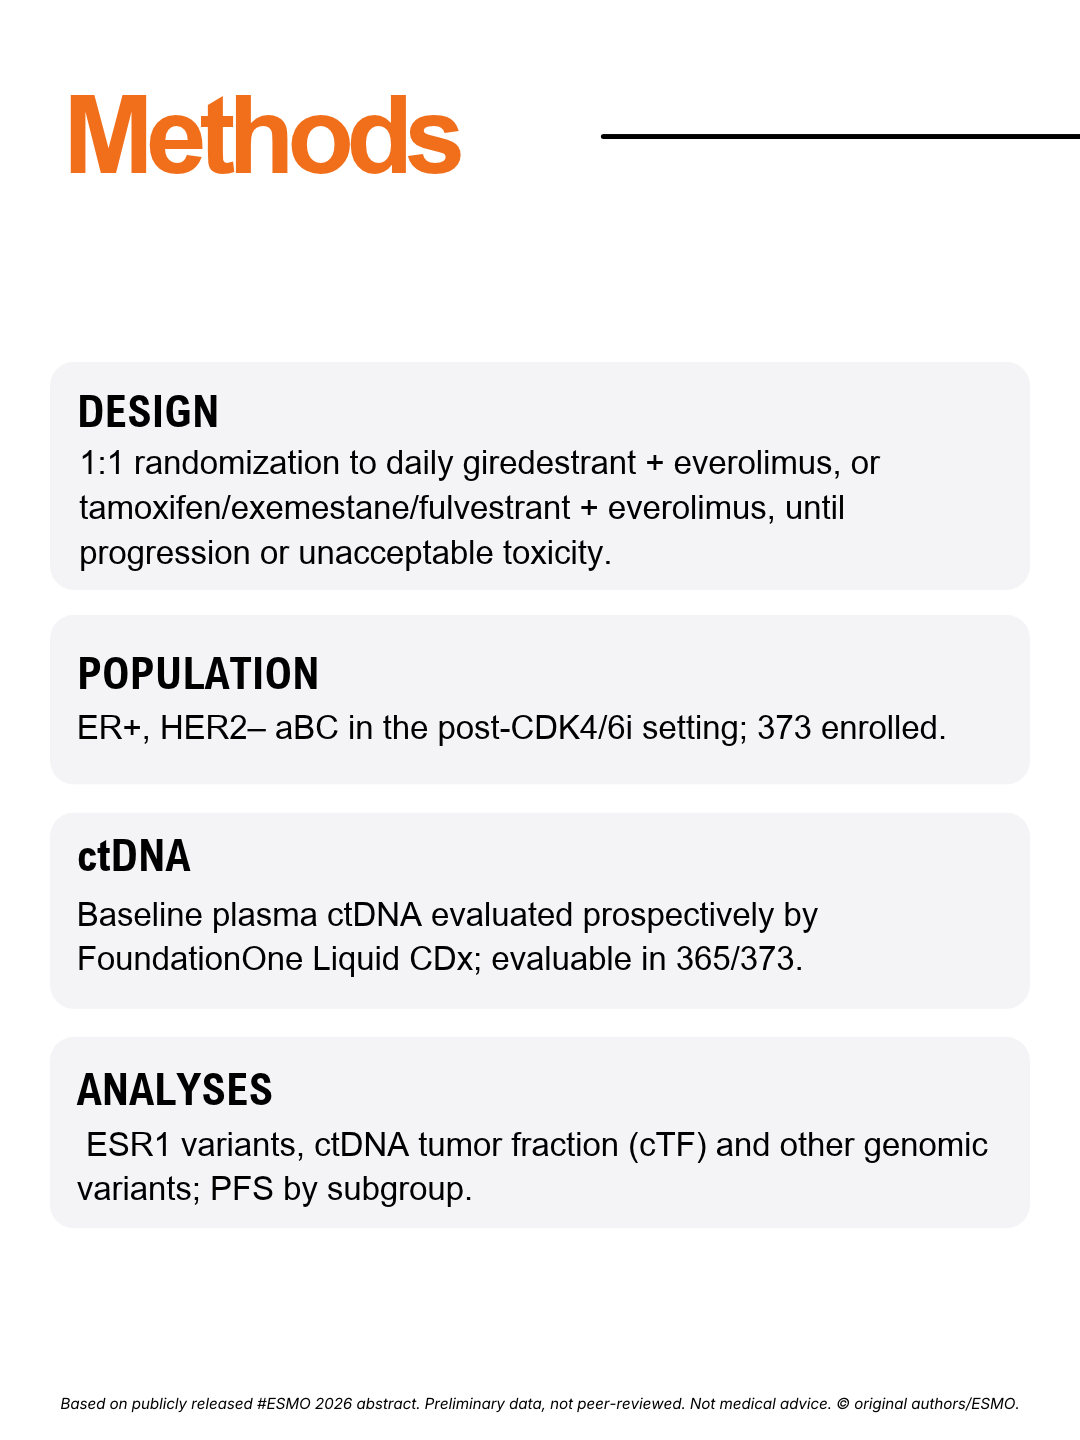
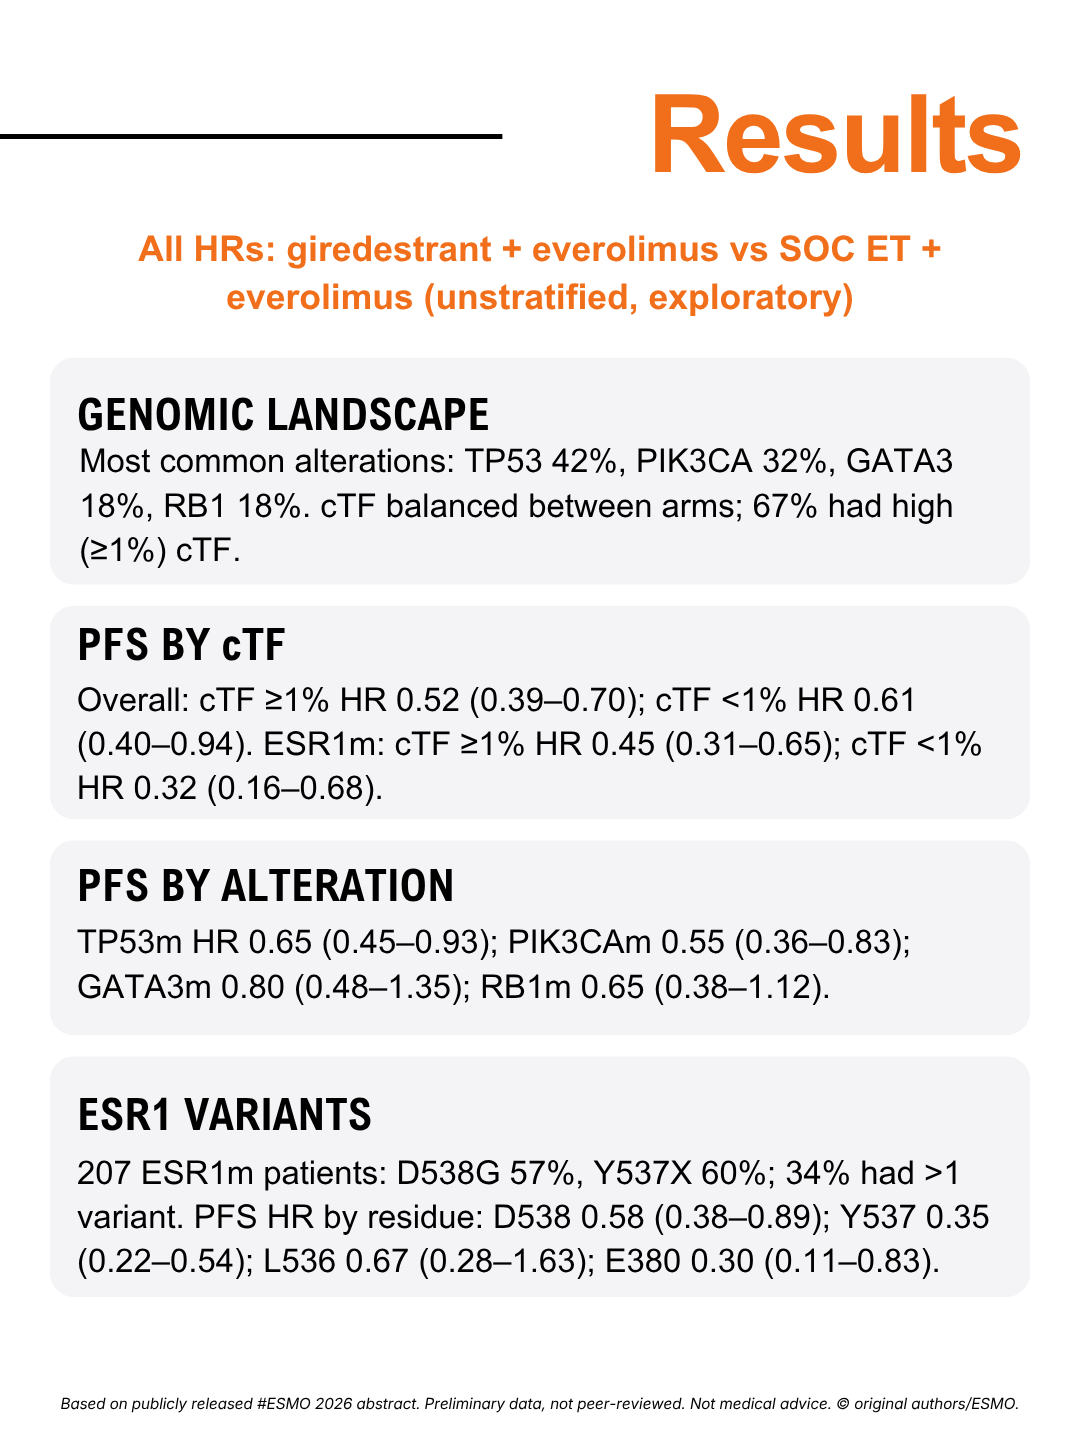
Exploratory biomarker analysis of phase III evERA (365 ctDNA-evaluable): giredestrant + everolimus vs SOC endocrine therapy + everolimus in post-CDK4/6i ER+, HER2– aBC.
PFS HR 0.52 (0.39–0.70) with cTF ≥1%; 0.61 (0.40–0.94) with cTF <1%
ESR1m: PFS HR 0.58 (D538) and 0.35 (Y537)
TP53m PFS HR 0.65 (0.45–0.93); PIK3CAm 0.55 (0.36–0.83)
Giredestrant + everolimus maintained greater PFS benefit regardless of cTF status, with benefit across all ESR1 variants and poor prognostic subgroups.

Sara Tolaney

DeLLphi-304

  • 1
  • 2
  • 3
  • 4
  • 5

In brief

OncoAlert 4Sight, #ESMO2026

Tarlatamab in Previously Treated SCLC: Extended Follow-Up of Overall Survival From the Phase 3 DeLLphi-304 Trial

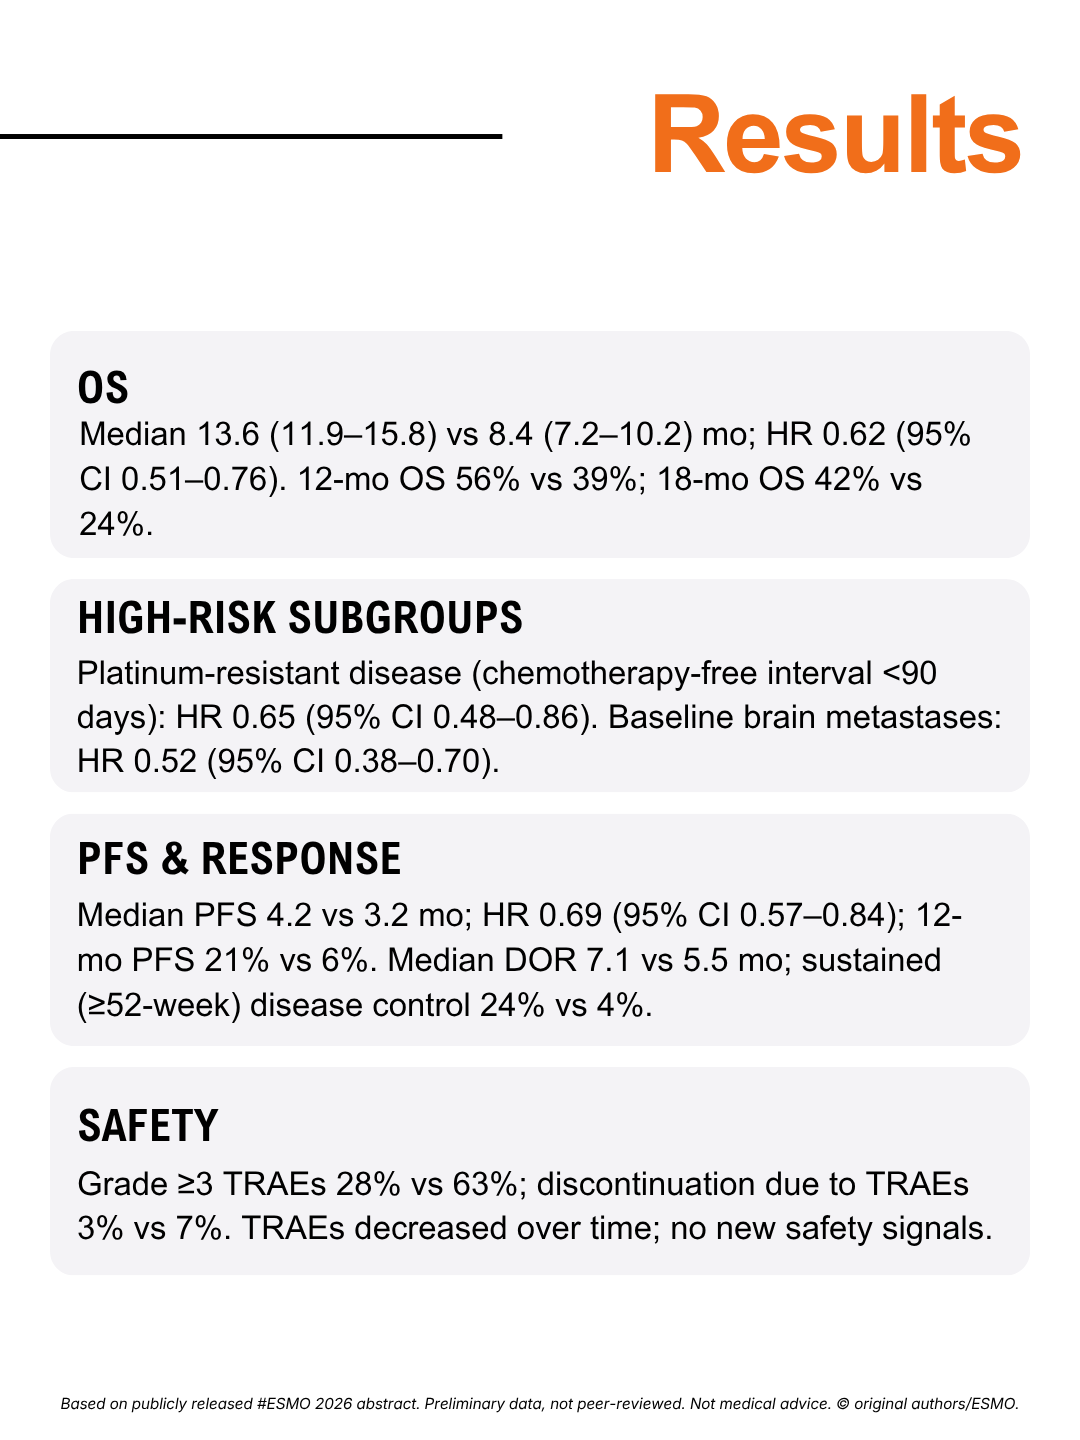
Phase 3 (n=509): tarlatamab vs chemotherapy (topotecan, lurbinectedin or amrubicin) in SCLC after first-line platinum-based chemotherapy. Primary endpoint: OS; median follow-up 23 mo.
Median OS 13.6 vs 8.4 mo; HR 0.62 (0.51–0.76); 18-mo OS 42% vs 24%
Baseline brain metastases subgroup: OS HR 0.52 (0.38–0.70)
Grade ≥3 TRAEs 28% vs 63%
Durable survival benefit with a manageable safety profile and no new safety signals, reinforcing tarlatamab as standard of care after first-line platinum-based chemotherapy.

Charles Rudin

Giannis Mountzios · Longhua Sun · Byoung Chul Cho · Umut Demirci · Sofia Baka · Mahmut Gümüş · Antonio Lugini · Bo Zhu · Yan Yu · Ippokratis Korantzis · Ji-Youn Han · Tudor-Eliade Ciuleanu · Myung-Ju Ahn · Pedro Rocha · Julien Mazières · Sally Lau · Martin Schuler · Fiona Blackhall · Tatsuya Yoshida · Taofeek Owonikoko · Luis Paz-Ares · Tony Jiang · Ali Hamidi · Diana Gauto · Gonzalo Recondo

LEAP-012

  • 1
  • 2
  • 3
  • 4
  • 5

In brief

OncoAlert 4Sight, #ESMO2026

Phase 3 LEAP-012 Study of Lenvatinib + Pembrolizumab vs Dual Placebo With Transarterial Chemoembolization (TACE) for Unresectable Non-Metastatic Hepatocellular Carcinoma: Long-Term OS Results

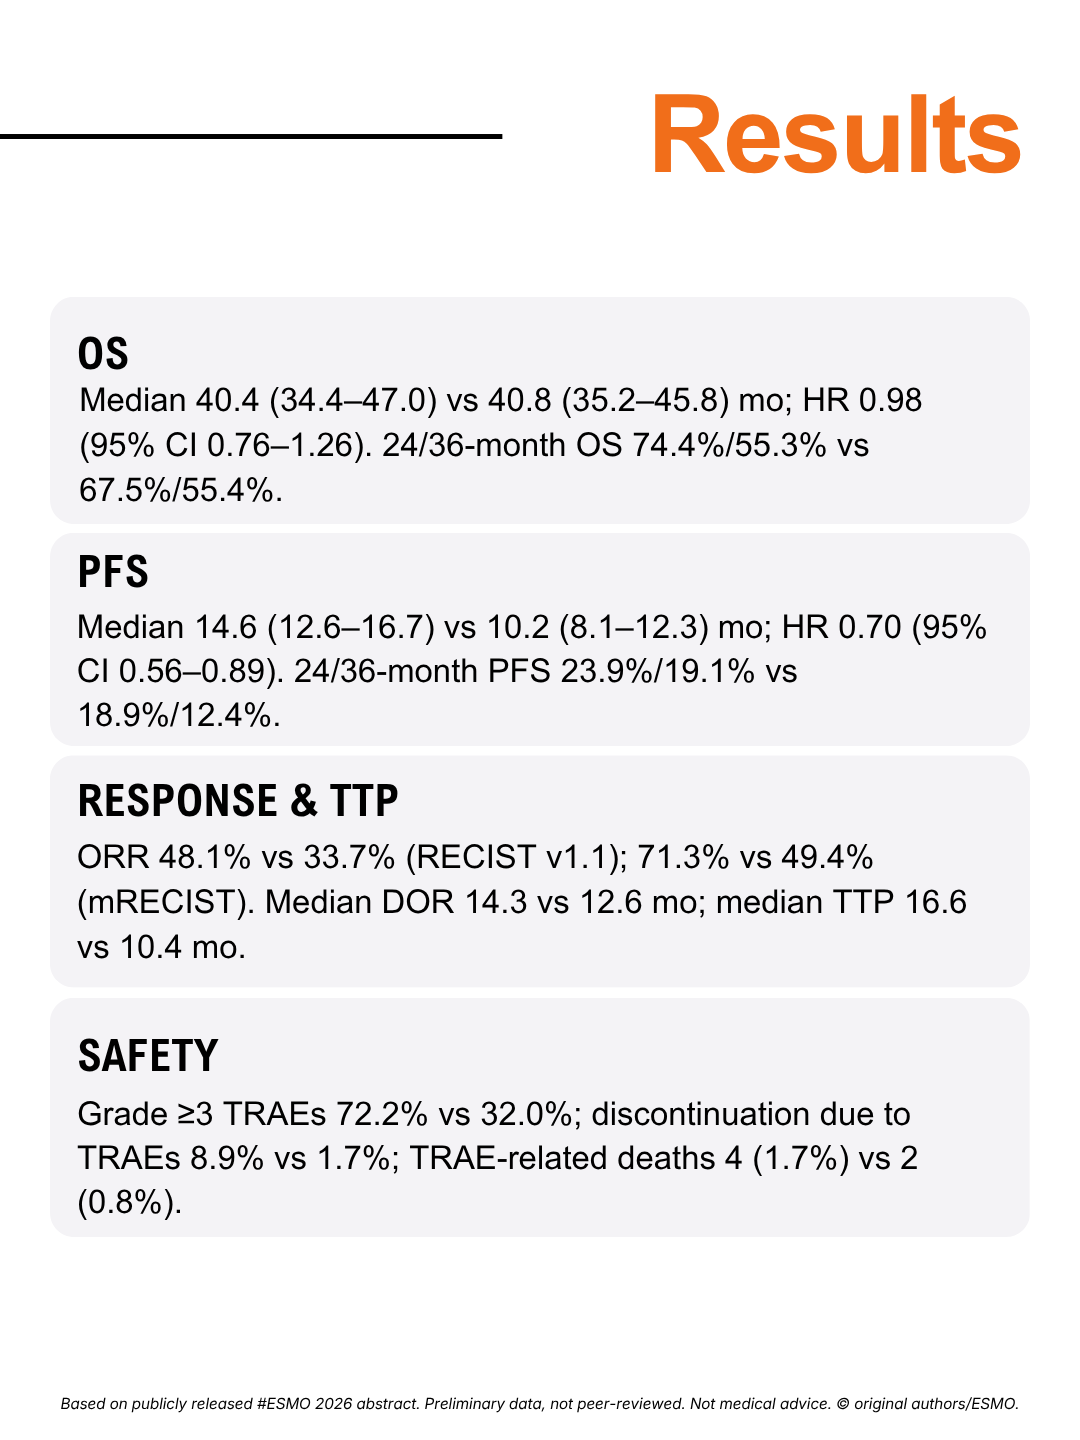
Phase 3 (n=480): lenvatinib + pembrolizumab + TACE vs dual placebo + TACE in unresectable, non-metastatic HCC. Dual primary endpoints: PFS and OS. Long-term OS (IA3).
Median OS 40.4 vs 40.8 mo; HR 0.98 (0.76–1.26)
Median PFS 14.6 vs 10.2 mo; HR 0.70 (0.56–0.89)
Grade ≥3 TRAEs 72.2% vs 32.0%
LEAP-012 met its primary endpoint for PFS but did not show OS benefit; a median OS of ~40 mo sets a new benchmark for trial design.

Josep Llovet

Masatoshi Kudo · Zhenggang Ren · Yabing Guo · Guohong Han · Hailan Lin · Jinfang Zheng · Sadahisa Ogasawara · Ji Hoon Kim · Haitao Zhao · Chuan Li · David Madoff · Mark Ghobrial · Tomokazu Kawaoka · René Gerolami · Masafumi Ikeda · Hiromitsu Kumada · Anthony El-Khoueiry · Arndt Vogel · Xiang Peng · Kalgi Mody · Corina Dutcus · Leonid Dubrovsky · Abby Siegel · Richard Finn

PEACE-1

  • 1
  • 2
  • 3
  • 4
  • 5

In brief

OncoAlert 4Sight, #ESMO2026

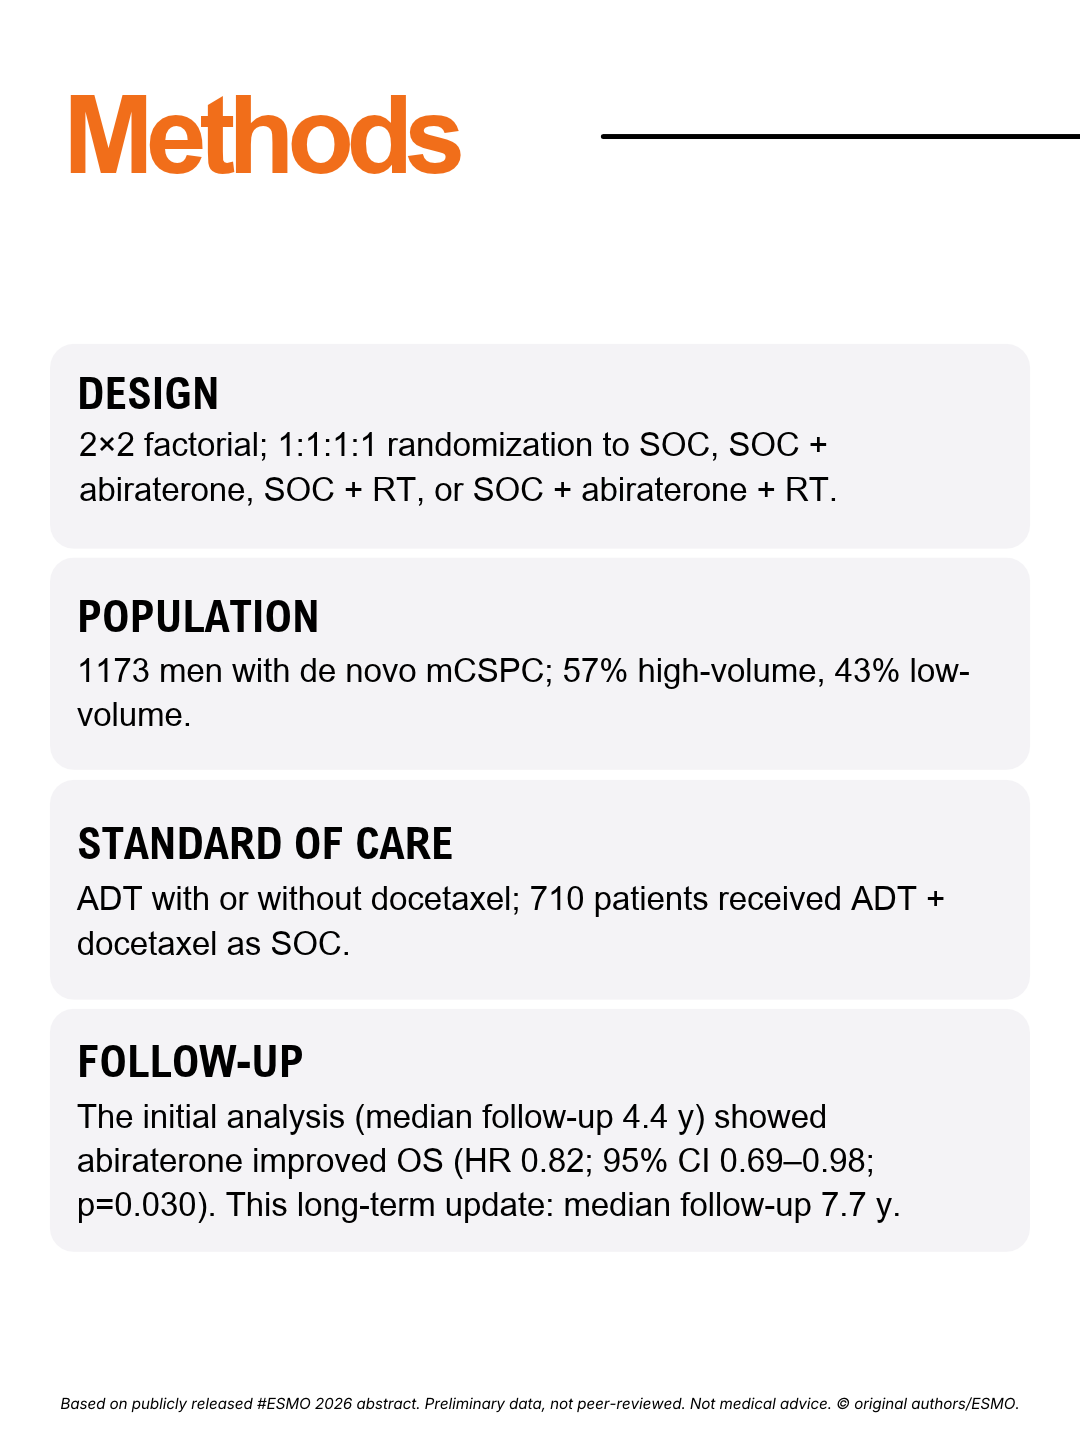
Long-Term Overall Survival With Abiraterone Acetate Plus Prednisone in the PEACE-1 Phase 3 Trial for De Novo Metastatic Castration-Sensitive Prostate Cancer (mCSPC)

Phase 3, 2×2 factorial (n=1173): abiraterone and/or prostate RT added to SOC (ADT ± docetaxel) in de novo mCSPC. Median follow-up 7.7 y.
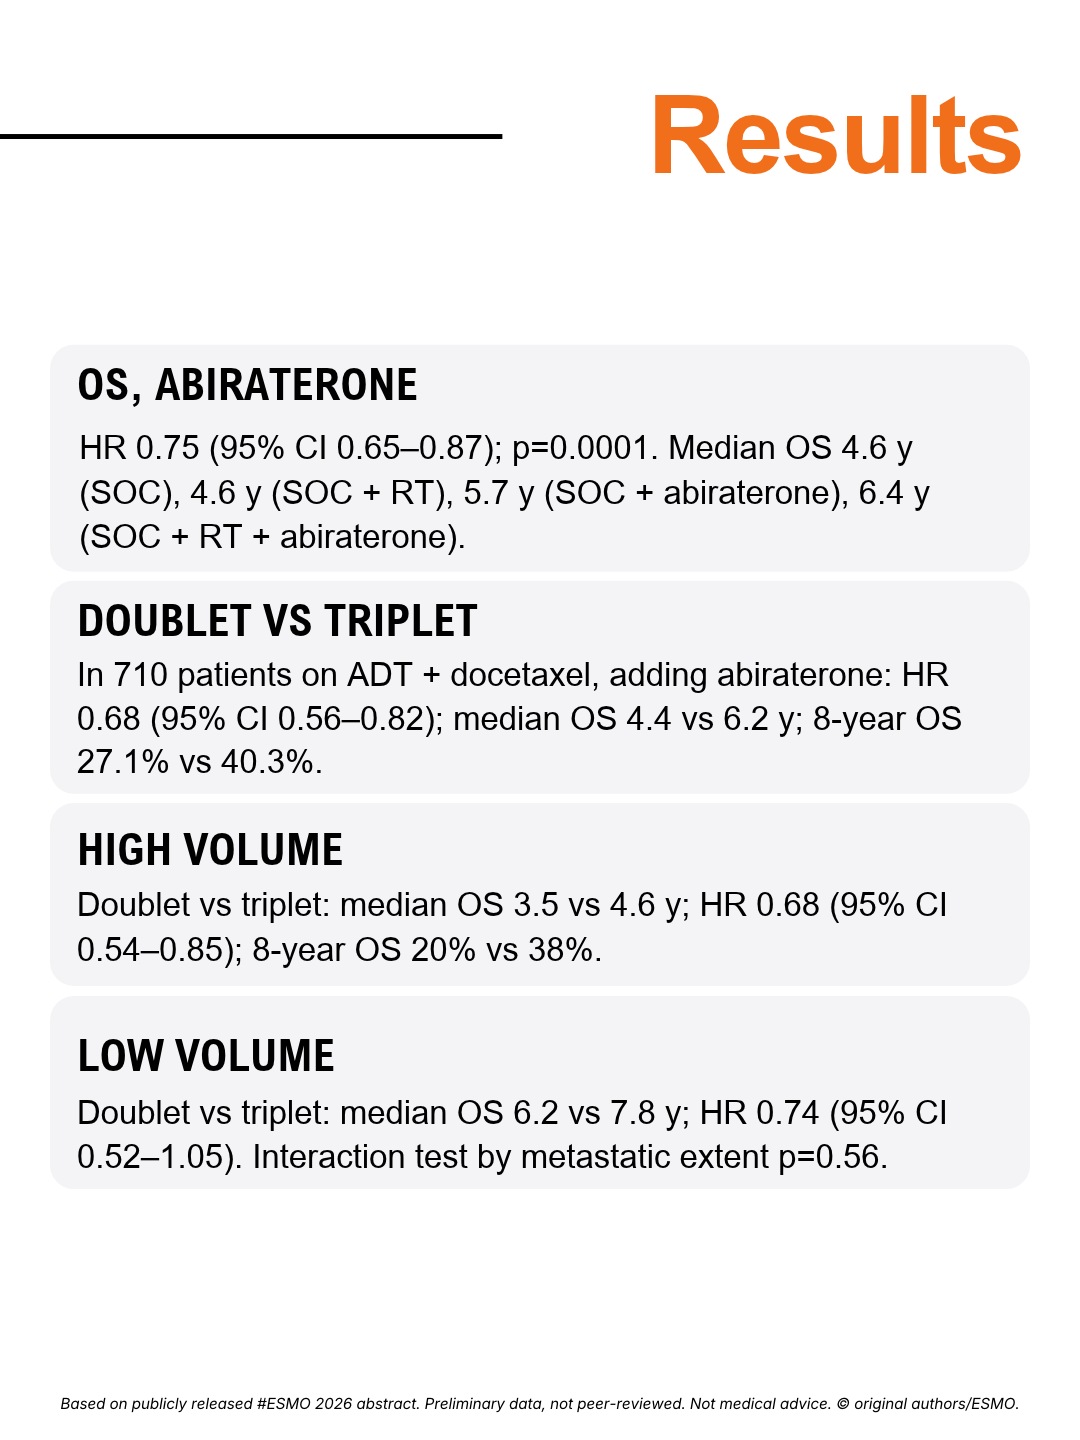
Abiraterone: OS HR 0.75 (0.65–0.87); p=0.0001
ADT + docetaxel ± abiraterone: median OS 4.4 vs 6.2 y; 8-year OS 27.1% vs 40.3%
High-volume: 8-year OS 20% vs 38%; interaction by metastatic extent p=0.56
Major OS benefit of adding abiraterone to SOC, irrespective of metastatic extent; triplet associated with almost twice as many long-term survivors in some subgroups.

Karim Fizazi

Stéphanie Foulon · Joan Carles · Guilhem Roubaud · Ray McDermott · Aude Fléchon · Bertrand Tombal · Stéphane Supiot · Dominik Berthold · Philippe Ronchin · Gabriel Kacso · Gwenaëlle Gravis · Fabio Calabro · Jean-François Berdah · Ali Hasbini · Marlon Silva · Antoine Thiery-Vuillemin · Igor Latorzeff · Loïc Mourey · Brigitte Laguerre · Sophie Abadie-Lacourtoisie · Etienne Martin · Claude El Kouri · Anne Escande · Alvar Rosello · Nicolas Magne · Friederike Schlurmann · Frank Priou · Marie-Eve Chand-Fouche · Salvador Villà Freixa · Muhammad Jamaluddin · Isabelle Rieger · Alberto Bossi

BRIDGET

  • 1
  • 2
  • 3
  • 4
  • 5

In brief

OncoAlert 4Sight, #ESMO2026

BRIDGET: A Phase II Trial of Tucatinib Added to Trastuzumab/Pertuzumab or Ado-Trastuzumab Emtansine After Isolated Intracranial Progression in Patients With Advanced HER2-Positive Breast Cancer

Single-arm phase II (47 evaluable): tucatinib added to ongoing HP or T-DM1 after SRS for isolated intracranial progression in HER2+ MBC. Primary endpoint: iPFS (RANO-BM).
Median iPFS not reached; p<0.0001 vs historical median of 5 mo
iPFS 91% at 6 mo, 64% at 12 mo, 59% at 18 mo
Grade ≥3 AEs 15%; extracranial progression 4.3%
Adding tucatinib to HP after radiation met the primary endpoint, with more than half of patients free of intracranial progression at 18 months.

Sarah Sammons

Amanda Van Swearingen · Laura Noteware · Nusayba Bagegni · Kelly Moulton · Stevie Threatt · Denise Jaggers · Shannon Shea · Eric Lipp · Erin Riley · Sin-Ho Jung · Gloria Broadwater · Masey Ross · Kimberly Strickland · Sasha Beyer · Alison Conlin · Aki Morikawa · Rashmi Murthy · Carey Anders

SARON

  • 1
  • 2
  • 3
  • 4
  • 5

In brief

OncoAlert 4Sight, #ESMO2026

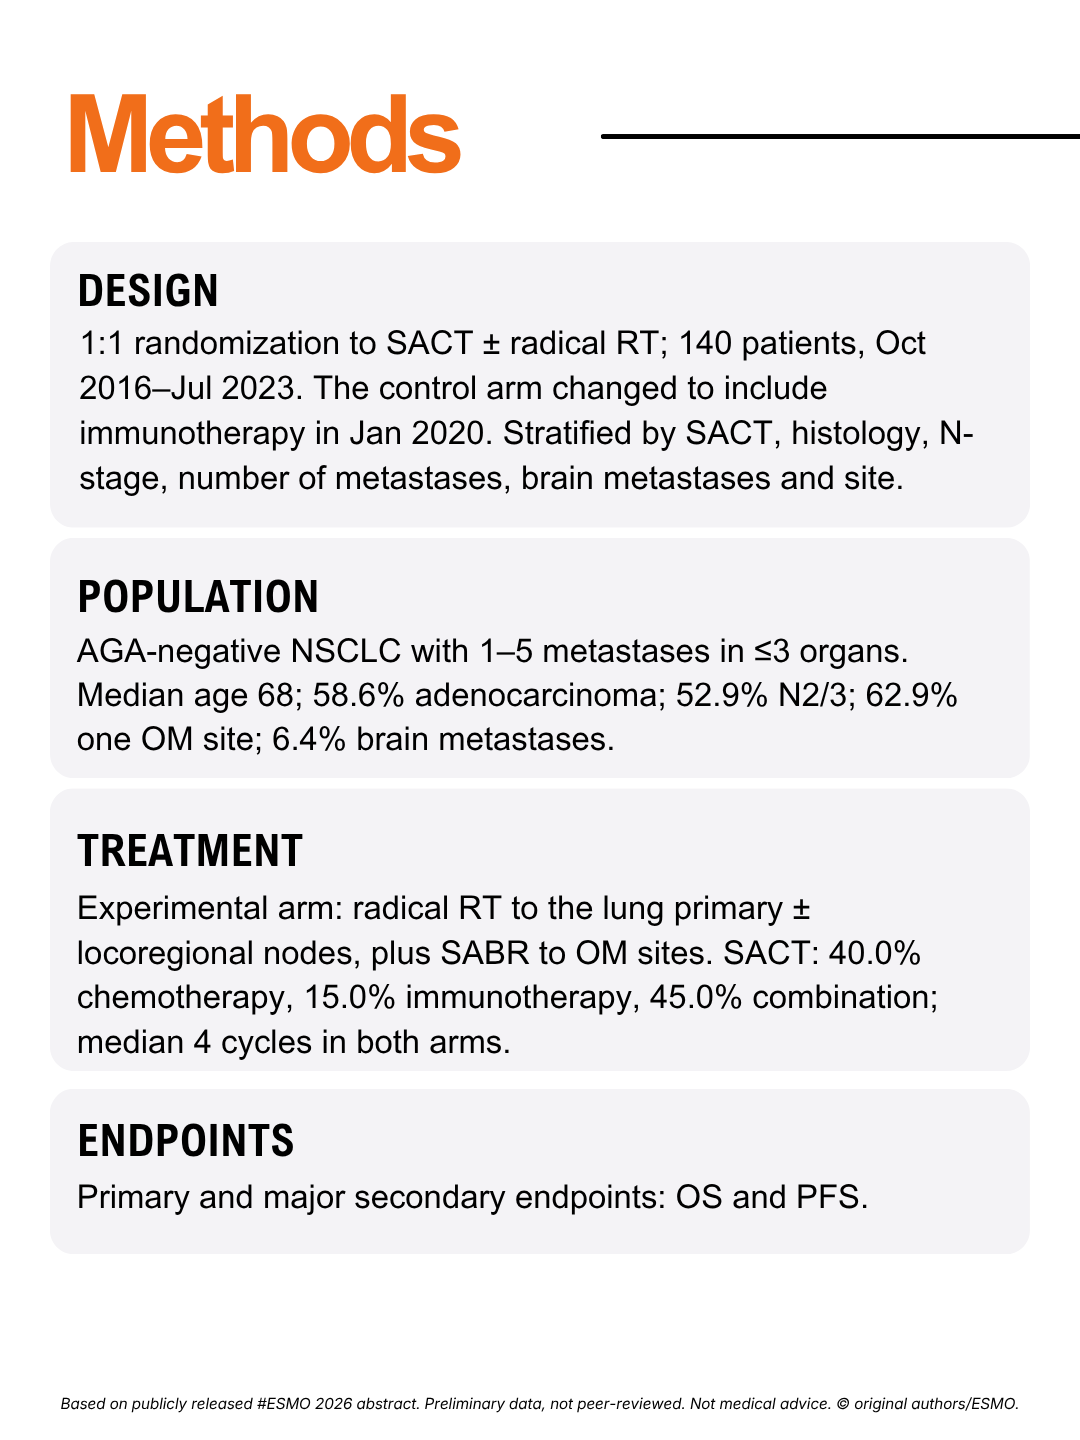
Primary Results of SARON: A Randomised-Controlled Trial of Consolidation Radiotherapy for Synchronous Oligometastatic Non-Small Cell Lung Cancer

Randomized phase II (n=140): first-line SACT ± consolidation radiotherapy in synchronous oligometastatic AGA-negative NSCLC. Endpoints: OS and PFS.
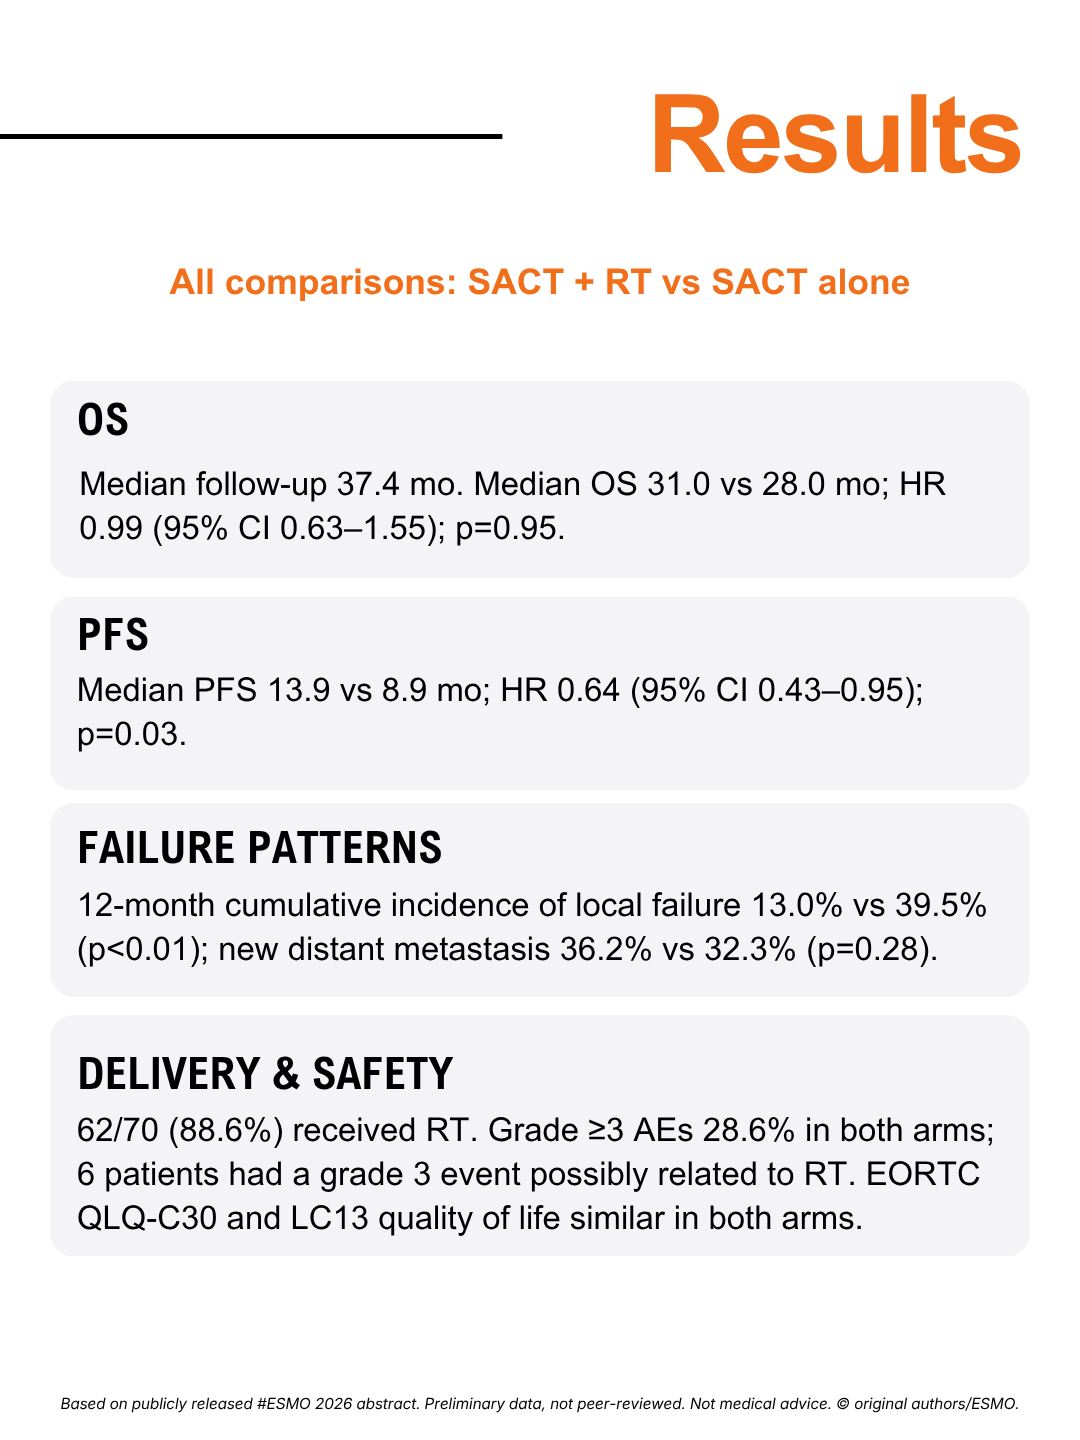
Median OS 31.0 vs 28.0 mo; HR 0.99 (0.63–1.55); p=0.95
Median PFS 13.9 vs 8.9 mo; HR 0.64 (0.43–0.95); p=0.03
12-month local failure 13.0% vs 39.5% (p<0.01); grade ≥3 AEs 28.6% in both arms
SACT + RT achieved better local disease control and longer PFS with acceptable side effects, but this did not translate into survival benefit.

Fiona McDonald

DEWI

  • 1
  • 2
  • 3
  • 4
  • 5

In brief

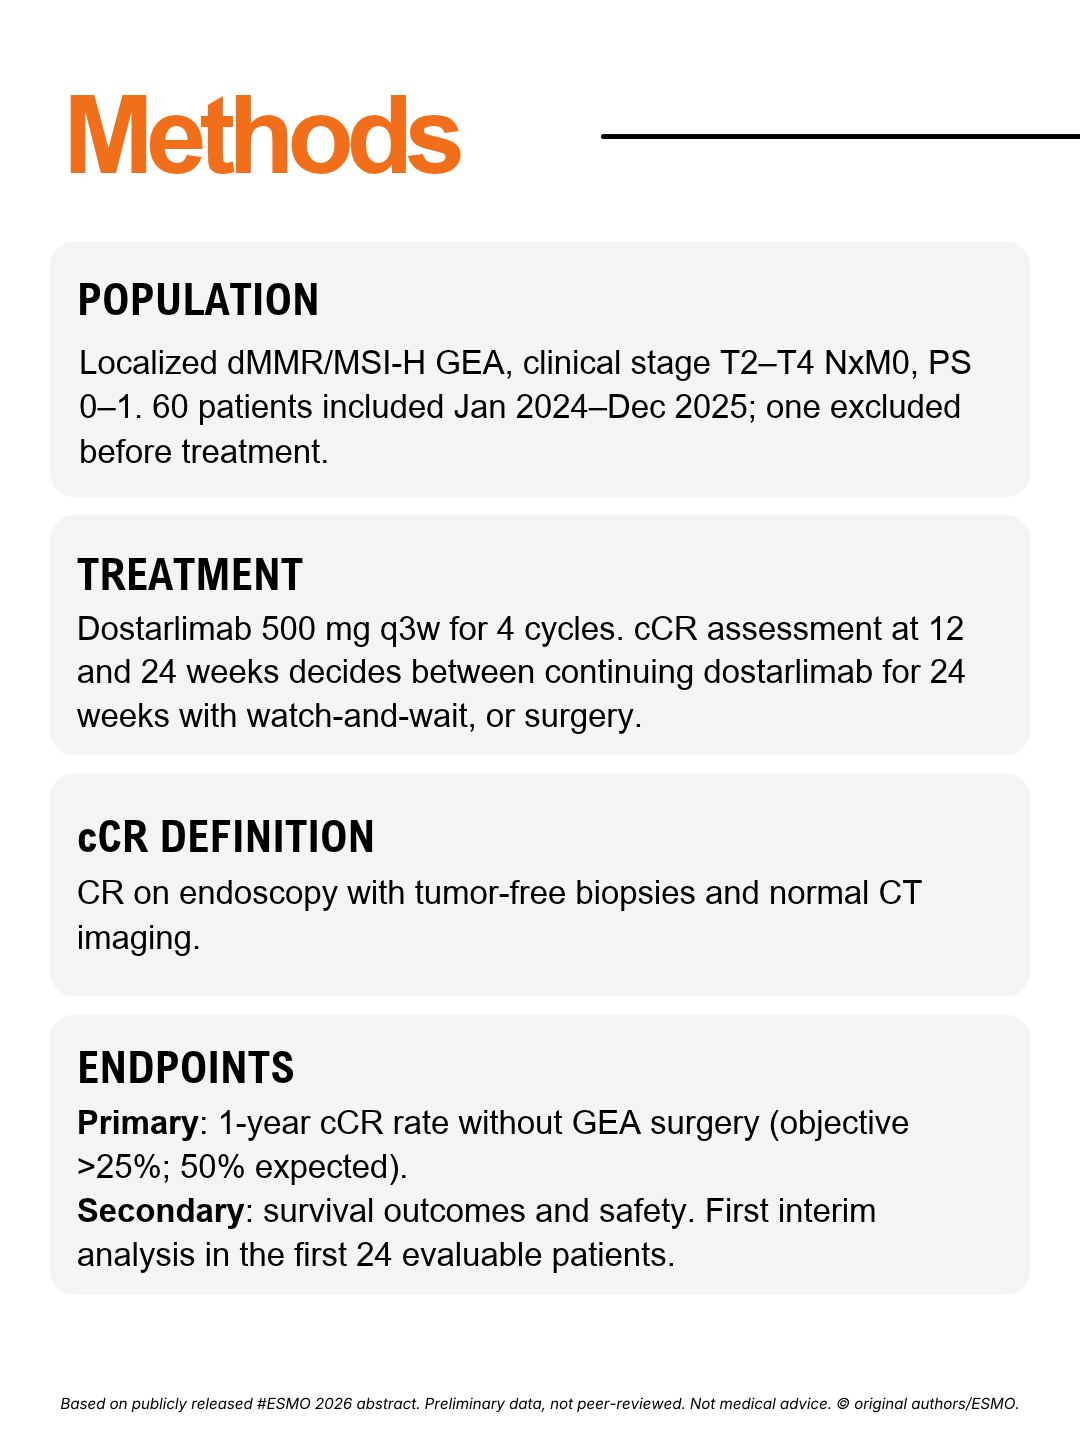
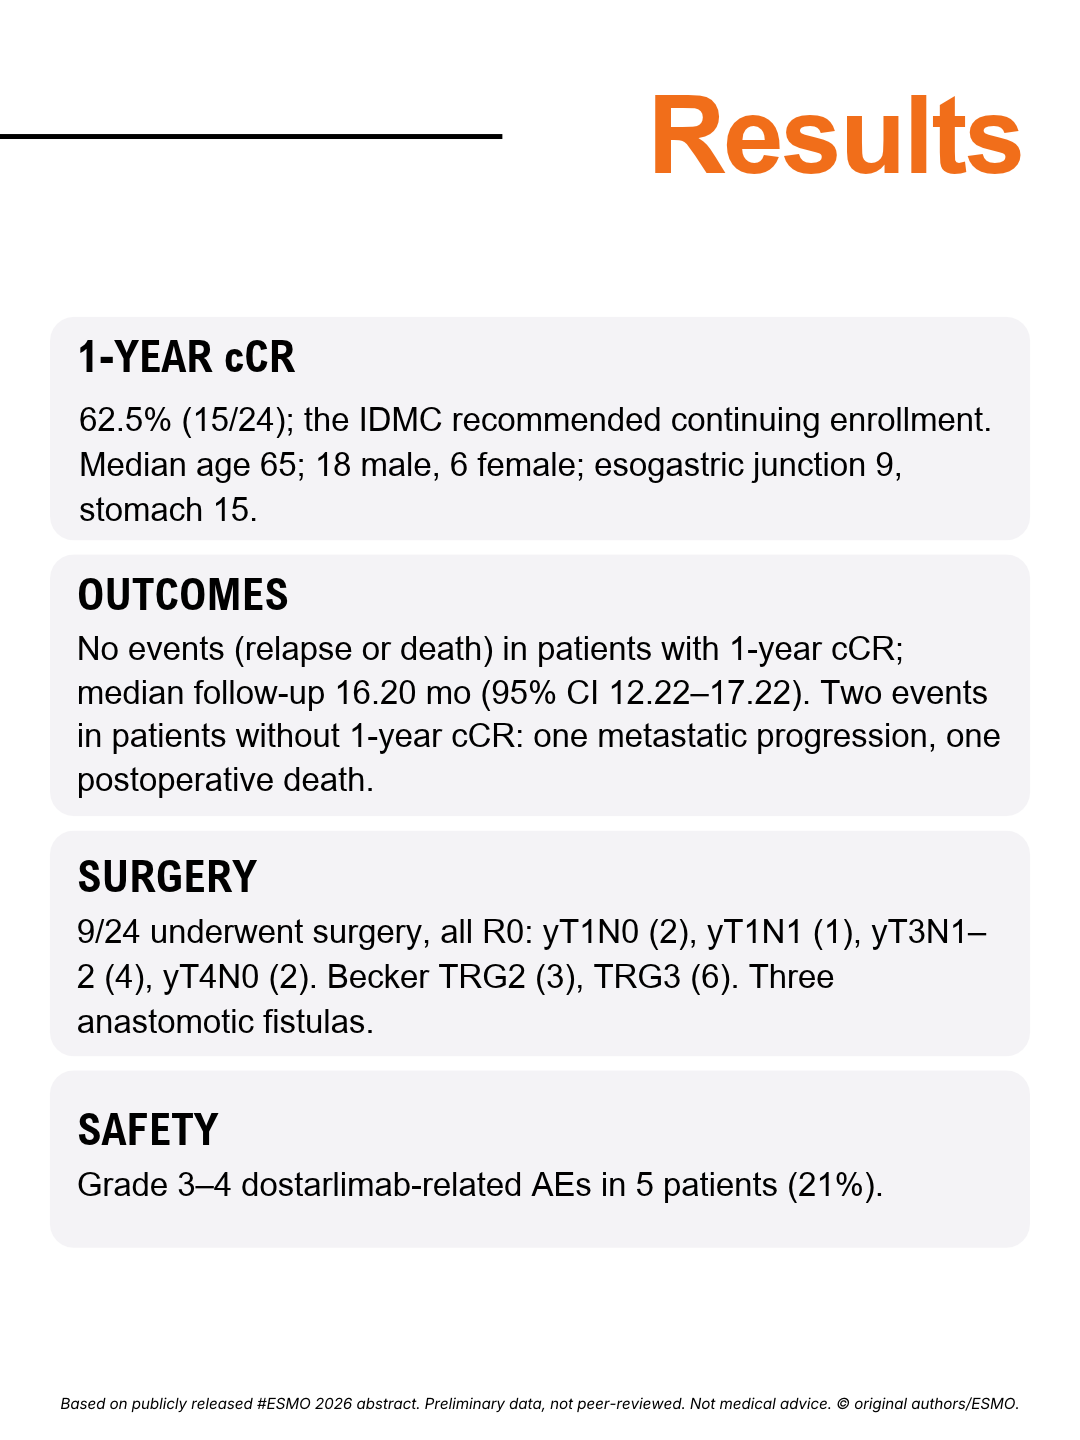
Watch-and-Wait Strategy for Dostarlimab in Localized dMMR/MSI-H Gastroesophageal Adenocarcinoma: Results From the First Interim Analysis of the GERCOR-GONO DEWI Phase II Study

Phase II, first interim analysis (24 evaluable patients): dostarlimab with a watch-and-wait strategy in localized dMMR/MSI-H gastroesophageal adenocarcinoma. Primary endpoint: 1-year cCR without surgery.

1-year cCR: 62.5% (15/24)
No relapse or death in patients with 1-year cCR (median follow-up 16.20 mo)
Grade 3–4 dostarlimab-related AEs: 21%; 9/24 underwent surgery, all R0
Dostarlimab led to a 62.5% 1-year cCR at the first interim analysis, enabling organ preservation.

Thierry André
Christelle de la Fouchardière

KEYNOTE-866

  • 1
  • 2
  • 3
  • 4
  • 5

In brief

OncoAlert 4Sight, #ESMO2026

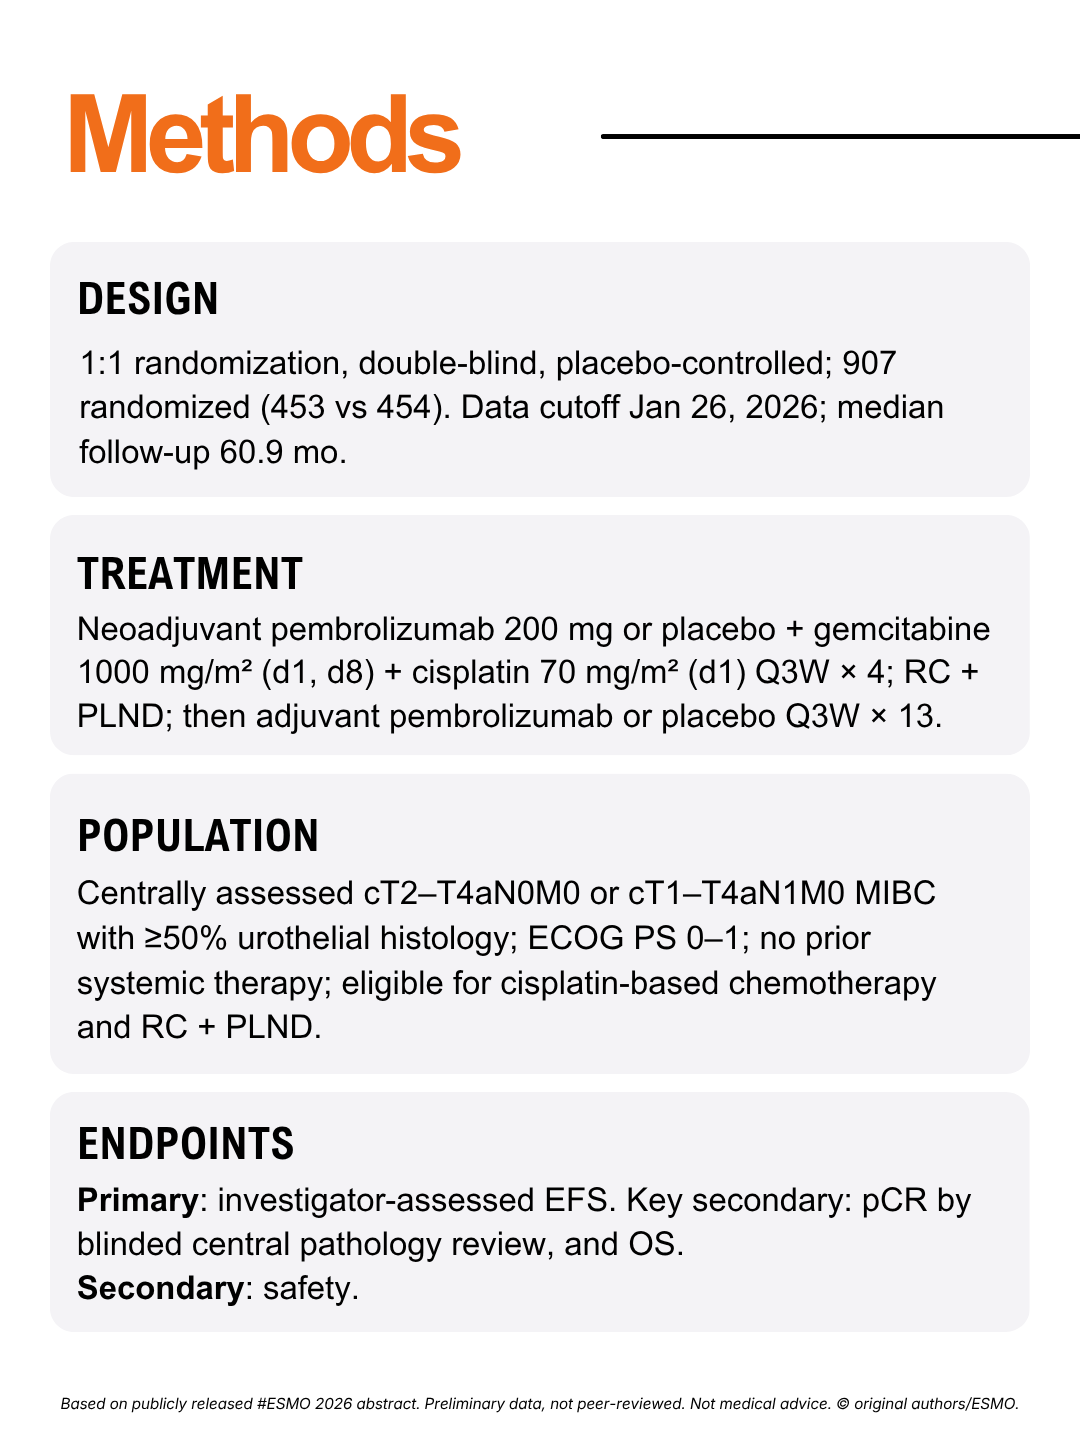
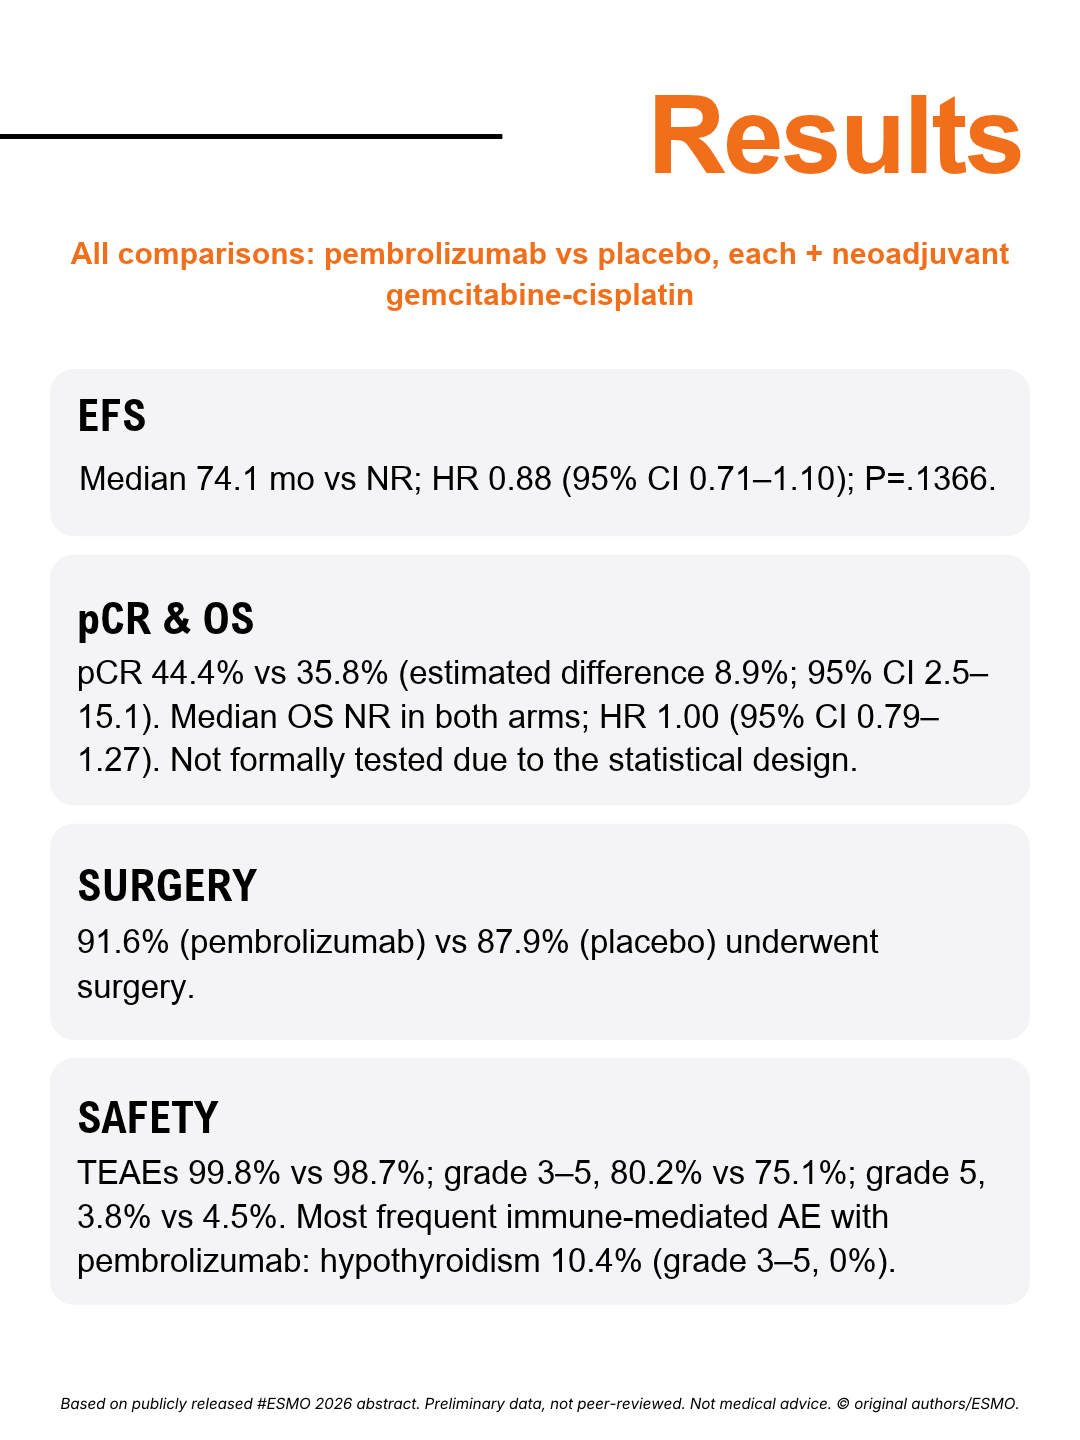
Perioperative Pembrolizumab or Placebo + Neoadjuvant Cisplatin and Gemcitabine in Muscle-Invasive Bladder Cancer: The Double-Blind, Phase 3 KEYNOTE-866 Study

Phase 3, double-blind (n=907): perioperative pembrolizumab or placebo + neoadjuvant gemcitabine-cisplatin and RC + PLND in cisplatin-eligible MIBC. Primary endpoint: EFS.
Median EFS 74.1 mo vs NR; HR 0.88 (0.71–1.10); P=.1366
pCR 44.4% vs 35.8%; OS HR 1.00 (0.79–1.27); neither formally tested
Grade 3–5 TEAEs 80.2% vs 75.1%
Perioperative pembrolizumab did not confer a statistically significant EFS benefit; safety profile manageable and consistent with prior reports.

Jens Bedke

Arlene Siefker-Radtke · Gary Steinberg · Hiroyuki Nishiyama · Xiao Fang · Ritesh Kataria · Blanca Homet Moreno · Christopher Hoimes

FOURLIGHT-1

  • 1
  • 2
  • 3
  • 4
  • 5

In brief

OncoAlert 4Sight, #ESMO2026

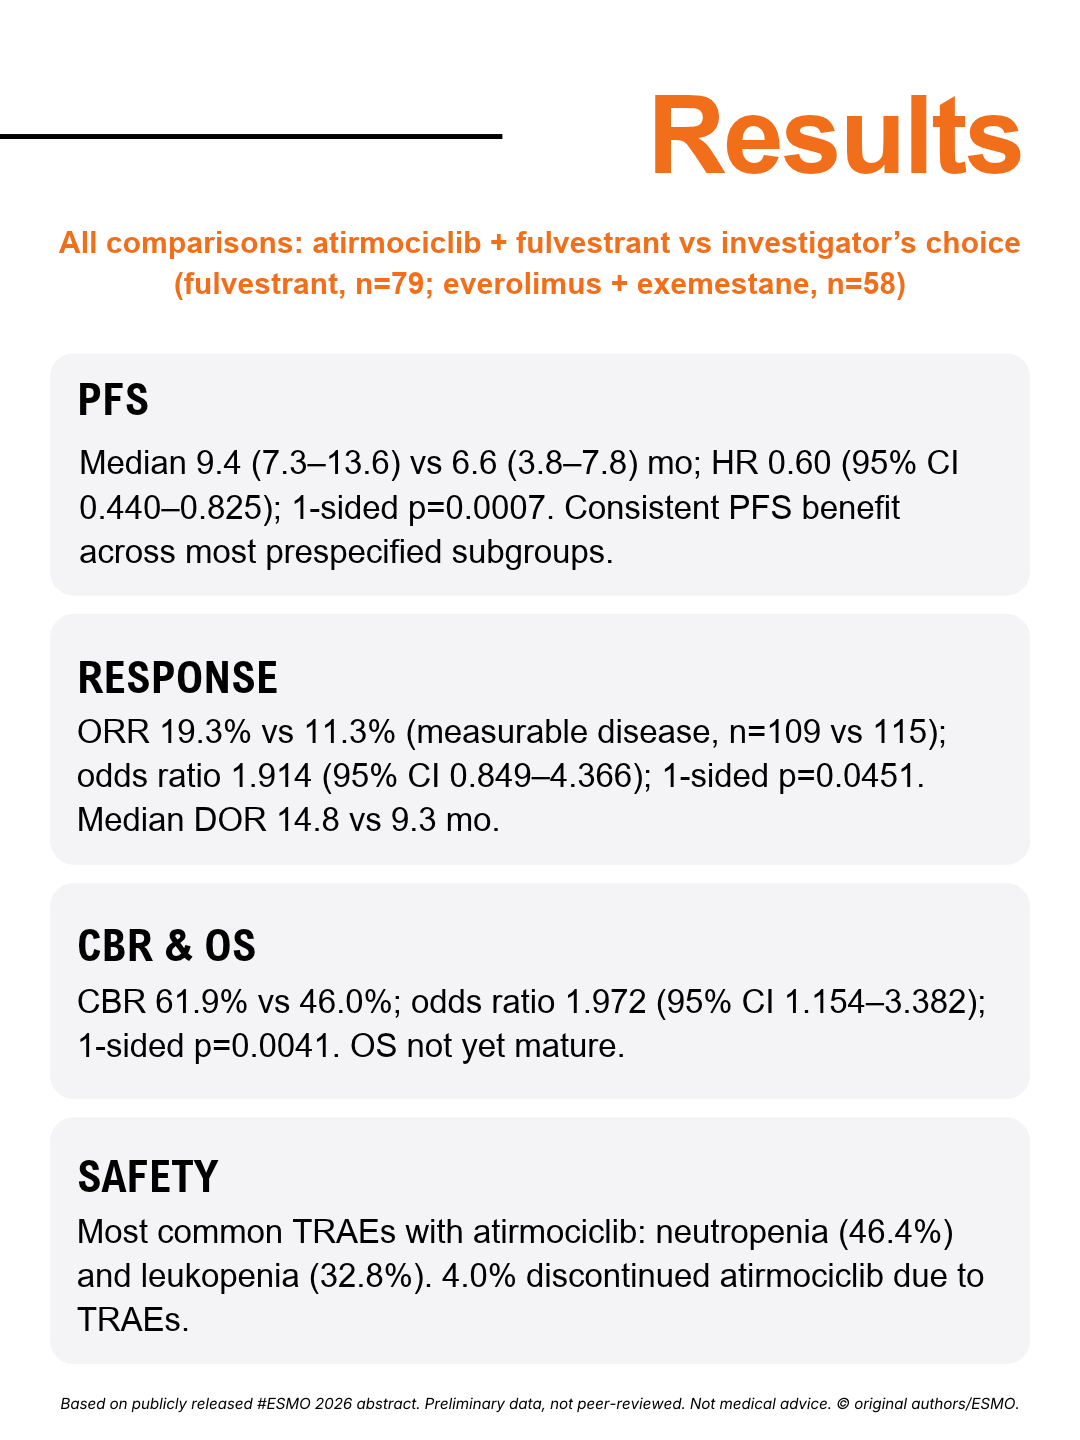
Efficacy and Safety of Atirmociclib + Fulvestrant in Patients With HR+/HER2– Advanced/Metastatic Breast Cancer Who Progressed on Prior CDK4/6 Inhibitor in a Randomized Phase 2 Study (FOURLIGHT-1)

Randomized phase 2 (n=263): atirmociclib + fulvestrant vs investigator’s choice (fulvestrant or everolimus + exemestane) in HR+/HER2– mBC after prior CDK4/6i. Primary: investigator-assessed PFS.

Median PFS 9.4 vs 6.6 mo; HR 0.60 (0.440–0.825); 1-sided p=0.0007
ORR in patients with measurable disease: 19.3% vs 11.3%; CBR: 61.9% vs 46.0%
Atirmociclib discontinuation due to TRAEs: 4.0%; most common TRAE neutropenia (46.4%)
First next-generation CDKi to show significant and clinically meaningful PFS improvement after prior CDK4/6i, with a manageable safety profile.

Antonio Giordano

PERSEE

  • 1
  • 2
  • 3
  • 4
  • 5

In brief

OncoAlert 4Sight, #ESMO2026

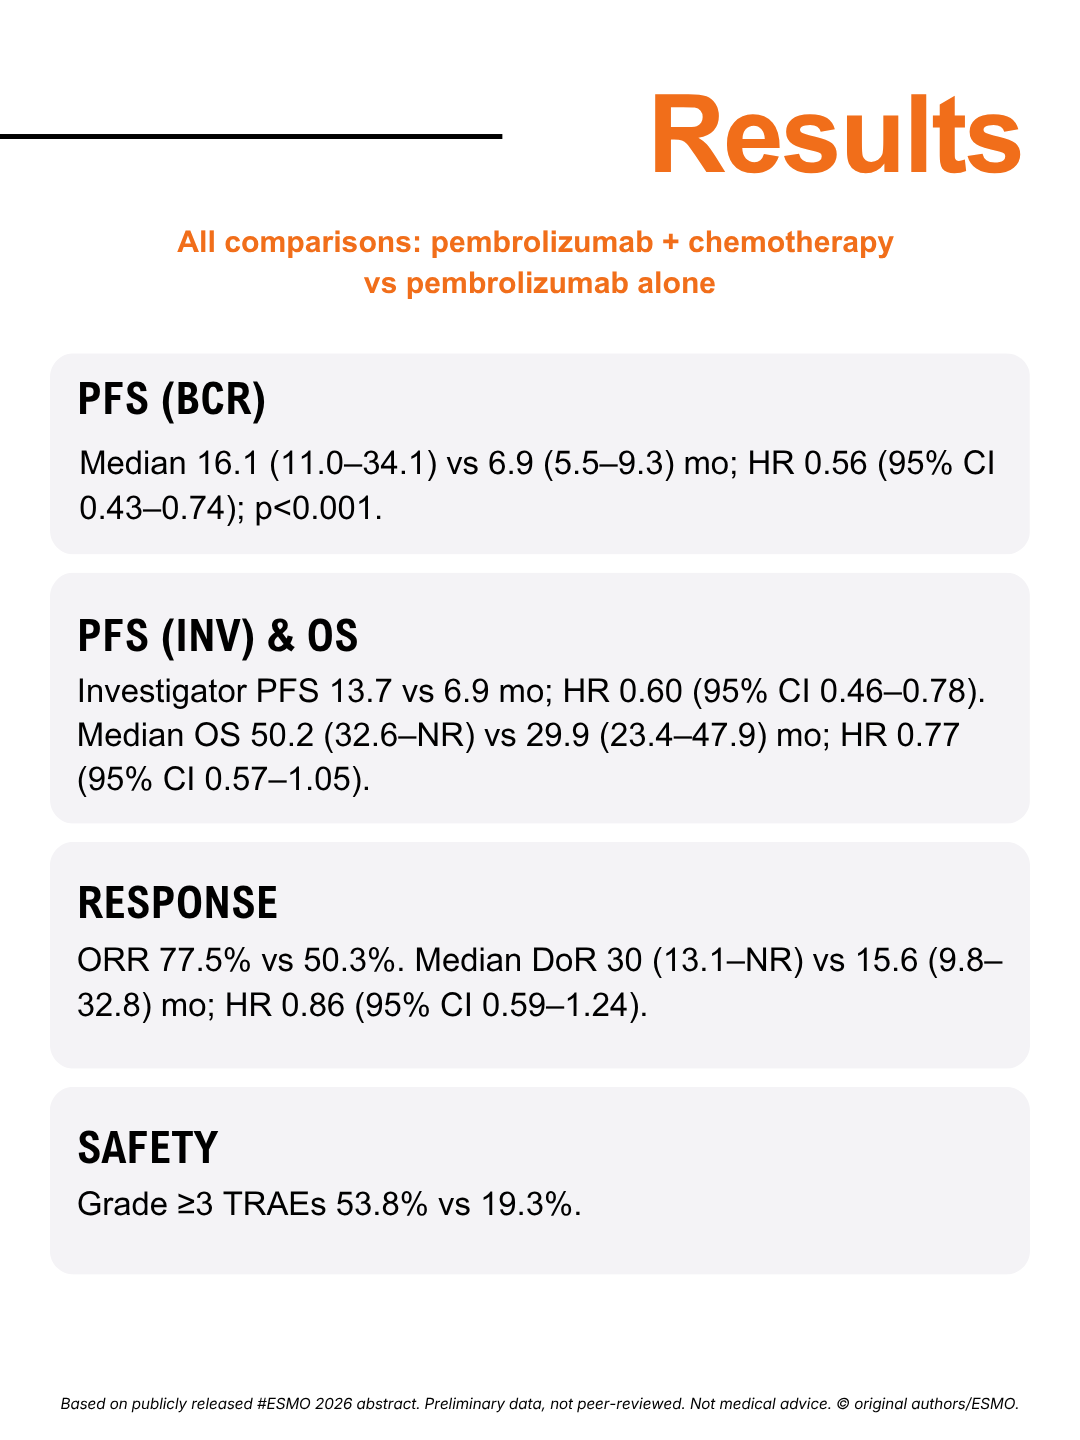
Pembrolizumab With or Without Platinum-Based Chemotherapy as First-Line Treatment in Advanced NSCLC With PD-L1 ≥50%: PERSEE Phase 3 Trial (GFPC 01-2020)

Phase 3, open-label (n=321): pembrolizumab + platinum-based chemotherapy vs pembrolizumab alone, first-line advanced NSCLC with PD-L1 ≥50%. Primary endpoint: PFS by blinded central review.

Median PFS 16.1 vs 6.9 mo; HR 0.56 (0.43–0.74); p<0.001
Median OS 50.2 vs 29.9 mo; HR 0.77 (0.57–1.05); ORR 77.5% vs 50.3%
Grade ≥3 TRAEs 53.8% vs 19.3%
Pembrolizumab-chemotherapy significantly improved PFS vs pembrolizumab monotherapy and may help refine treatment selection.

Chantal Decroisette

Renaud Descourt · Christos Chouaid · Maurice Pérol · Benjamin Besse · Laurent Greillier · Olivier Bylicki · Charles Ricordel · Florian Guisier · Radj Gervais · Roland Schott · Jean-Bernard Auliac · Gilles Robinet

LITESPARK-012

  • 5
  • 1
  • 2
  • 3
  • 4

In brief

OncoAlert 4Sight, #ESMO2026

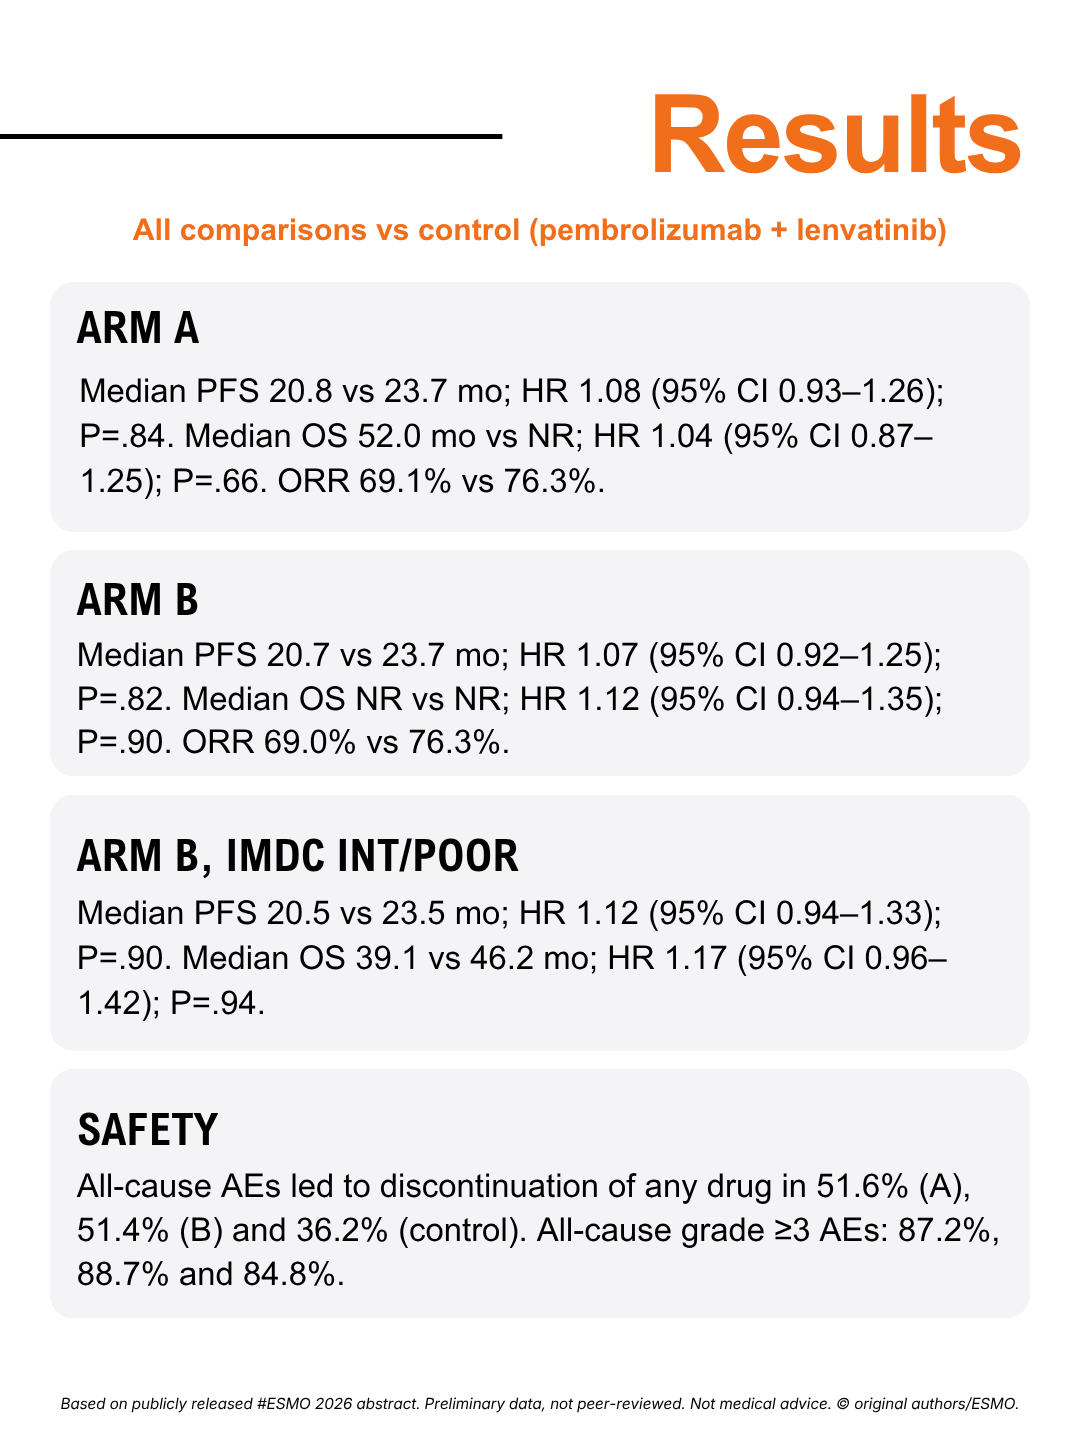
First-Line Pembrolizumab + Lenvatinib + Belzutifan or MK-1308A + Lenvatinib in Advanced RCC: The Randomized Open-Label Phase 3 LITESPARK-012 Study

Phase 3 (n=1688), untreated advanced ccRCC: pembrolizumab + lenvatinib + belzutifan (Arm A) or MK-1308A + lenvatinib (Arm B) vs pembrolizumab + lenvatinib. Dual primary: PFS by BICR and OS.

Arm A: PFS HR 1.08 (0.93–1.26); OS HR 1.04 (0.87–1.25)
Arm B: PFS HR 1.07 (0.92–1.25); OS HR 1.12 (0.94–1.35)
Discontinuation due to AEs: 51.6% (A), 51.4% (B), 36.2% (control)
Neither belzutifan nor CTLA-4 blockade added to pembrolizumab + lenvatinib improved efficacy; pembrolizumab + lenvatinib remains a 1L SOC.

Toni Choueiri

Thomas Powles · Martin Voss · Elizabeth Plimack · Howard Gurney · Yue Song · Rodolfo Perini · Karla Rodriguez-Lopez · Brian Rini

postMONARCH

  • 1
  • 2
  • 3
  • 4
  • 5

In brief

OncoAlert 4Sight, #ESMO2026

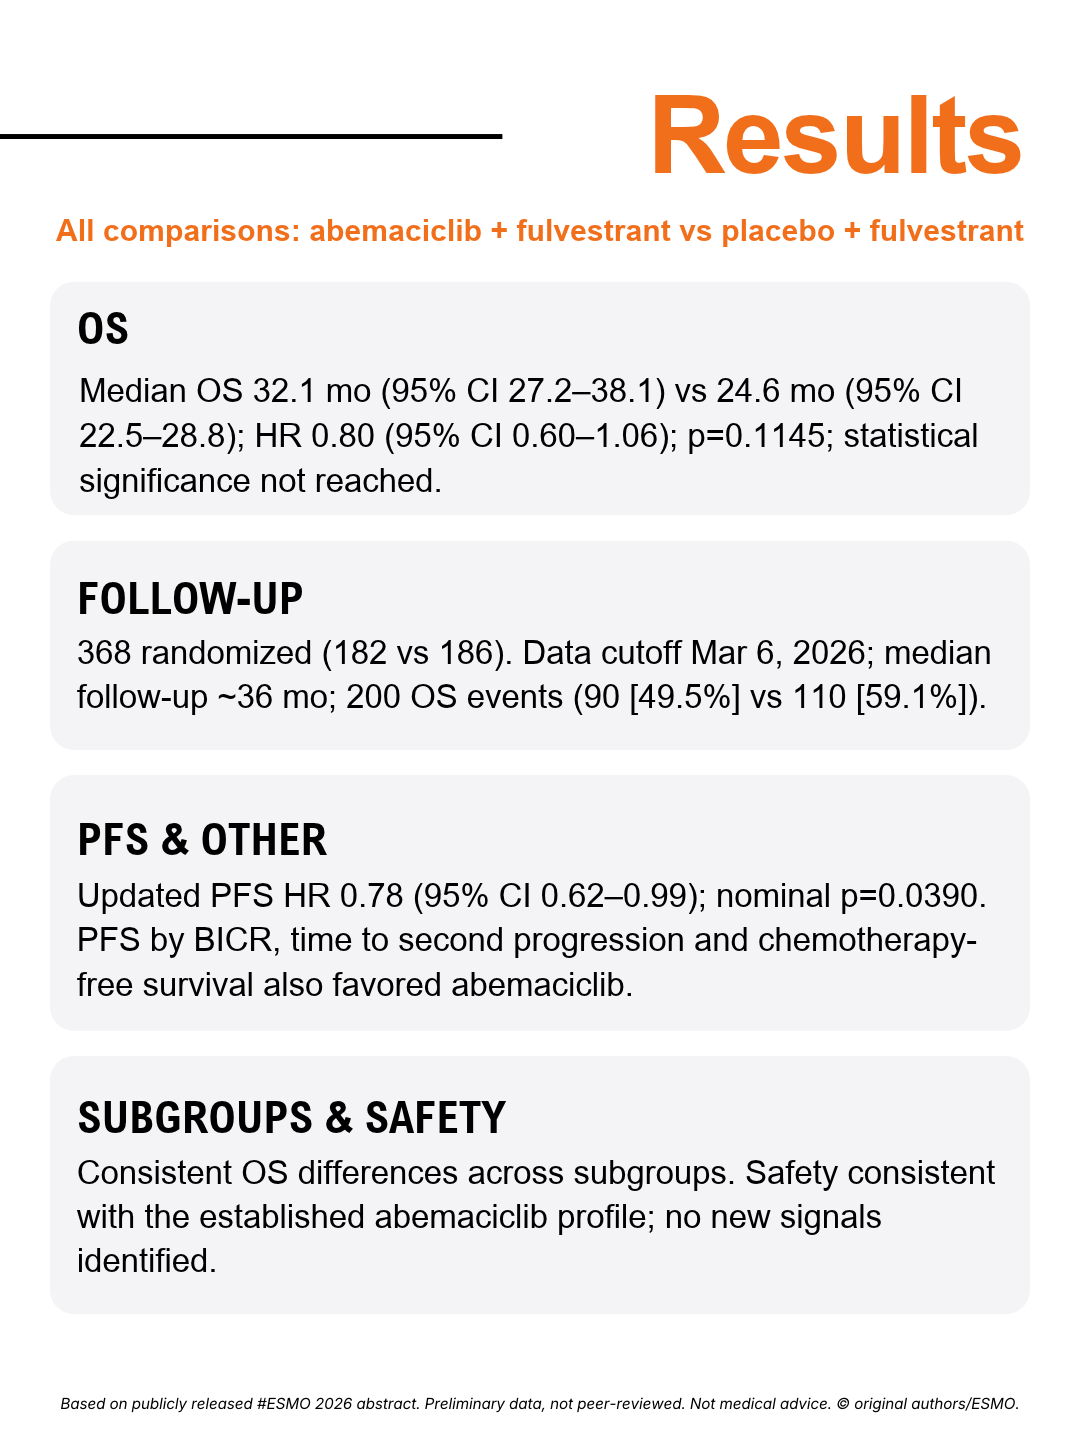
Final Overall Survival Analysis of postMONARCH: Abemaciclib Plus Fulvestrant After Progression on Prior CDK4/6 Inhibitor in HR+, HER2– Advanced Breast Cancer

Phase 3, double-blind trial (n=368): abemaciclib or placebo plus fulvestrant in HR+, HER2– ABC after progression on prior CDK4/6i + ET. Final OS analysis.

Median OS 32.1 vs 24.6 mo; HR 0.80 (0.60–1.06); p=0.1145, statistical significance not reached
Updated PFS HR 0.78 (0.62–0.99); nominal p=0.0390
Safety consistent with the established abemaciclib profile; no new signals
Numerically longer median OS, not statistically significant. While absolute PFS benefit was modest, overall evidence supports considering abemaciclib-based treatment after disease progression on prior CDK4/6i + ET.

Kevin Kalinsky

Giampaolo Bianchini · Erika Hamilton · Stephanie Graff · Kyong Hwa Park · Rinath Jeselsohn · Umut Demirci · Miguel Martin · Rachel Layman · Sara Hurvitz · Sarah Sammons · Peter Kaufman · Montserrat Muñoz · Jiun-I Lai · Holly Knoderer · Cynthia Sandoval · Aarti Chawla · Bastien Nguyen · Yanhong Zhou · Elizabeth Ravenberg · Lacey Litchfield · Lillian Smyth · Seth Wander

GIM3 FATA

  • 11
  • 2
  • 3
  • 4
  • 5

In brief

OncoAlert 4Sight, #ESMO2026

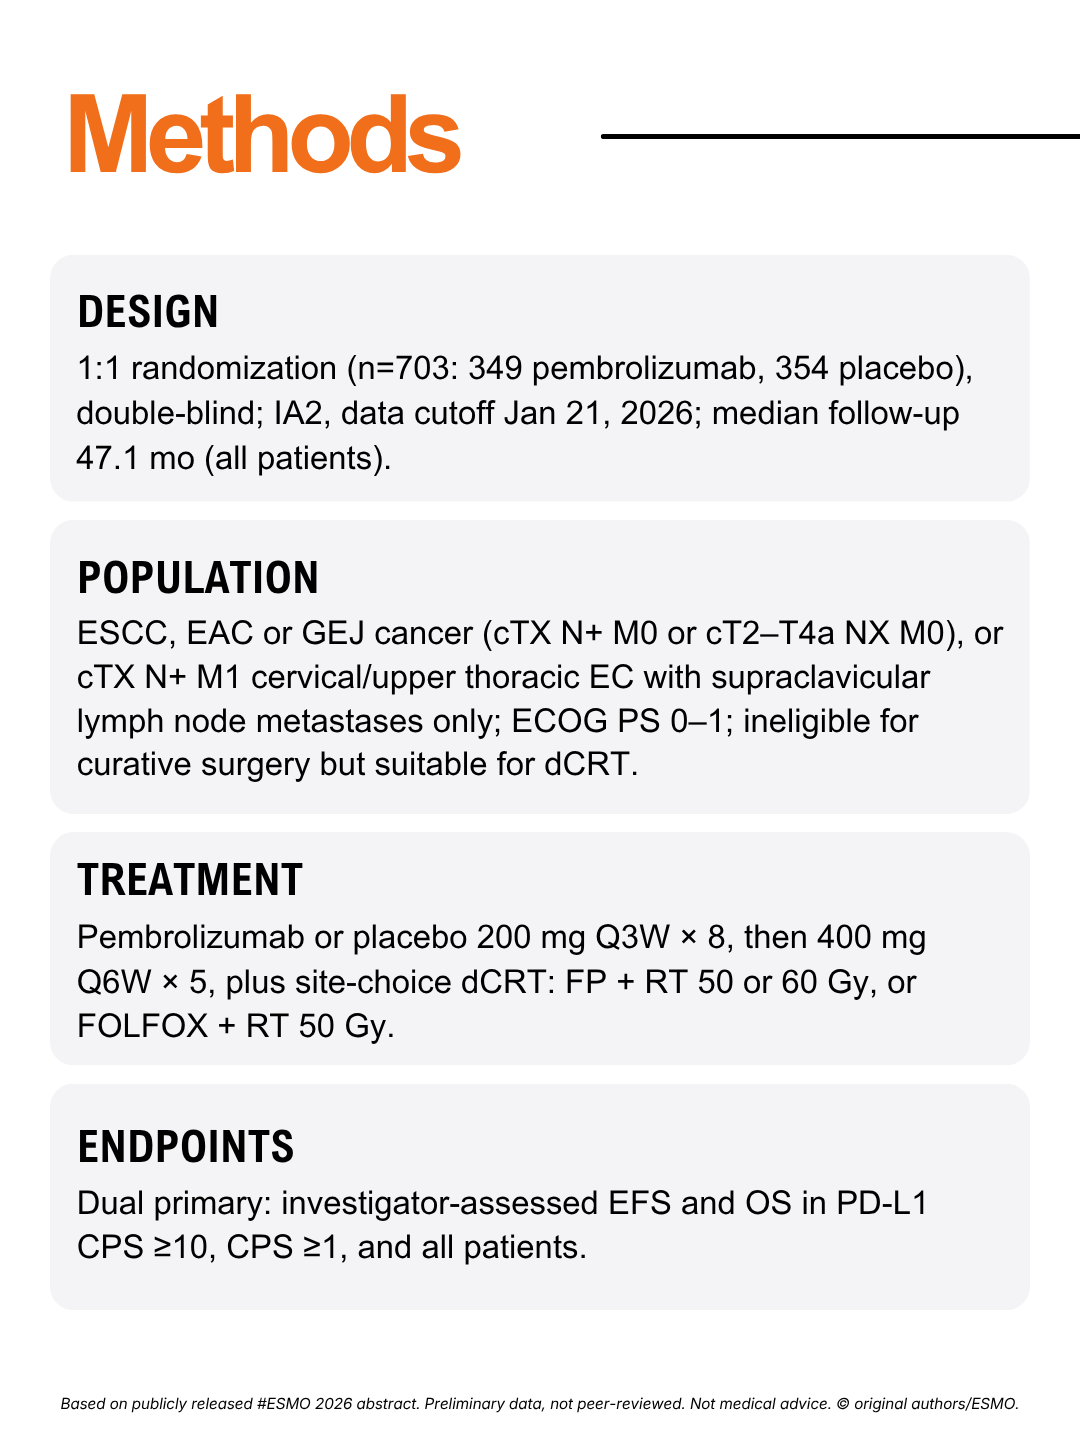
Pembrolizumab or Placebo Plus Concurrent Definitive Chemoradiotherapy in Esophageal and Gastroesophageal Junction (GEJ) Cancer: The Phase 3 Randomized KEYNOTE-975 Study

Phase 3, double-blind trial (n=703): pembrolizumab or placebo plus definitive chemoradiotherapy in untreated, unresectable esophageal/GEJ cancer. Dual primary endpoints: EFS and OS.

CPS ≥10 EFS: median 15.2 vs 14.7 mo; HR 0.97 (0.77–1.23); P=0.3994
CPS ≥10 OS: median 32.2 vs 35.0 mo; HR 1.00 (0.77–1.30); nominal P=0.5003
Grade 5 AEs 13% vs 10%; discontinuation due to AEs 34% vs 27%
Pembrolizumab + dCRT did not significantly improve EFS in PD-L1 CPS ≥10; no new safety signals observed.

Manish Shah

Jaafar Bennouna · Toshihiko Doi · Lin Shen · Ken Kato · Antoine Adenis · Harvey Mamon · Markus Moehler · Xiaolong Fu · Byoung Chul Cho · Sonal Bordia · Pooja Bhagia · Chie-Schin Shih · Anjali Desai · Peter Enzinger

KEYNOTE-975

  • 5
  • 1
  • 2
  • 3
  • 4

In brief

OncoAlert 4Sight, #ESMO2026
Final Analysis of the GIM3 FATA Trial: Treatment Schedule and Three Aromatase Inhibitors in Postmenopausal HR+ Early Breast Cancer

Randomized trial (n=3697): 5 years of anastrozole, exemestane or letrozole, upfront or after 2 years of tamoxifen. Co-primary: DFS by schedule and by AI.

Upfront vs switch: DFS HR 0.95 (0.82–1.09); OS HR 0.88 (0.74–1.06)
10-year DFS 79.1% anastrozole, 76.6% letrozole, 74.2% exemestane (global p=0.028)
Exemestane vs anastrozole: adjusted DFS HR 1.23 (1.04–1.46). 10-year OS across AIs: no statistically significant difference (p=0.25)
No schedule superior; exemestane associated with worse DFS. Choice should be individualized by tolerability, comorbidities and cost.

Pietro De Placido

Laura Arenare · Erica Pietroluongo · Giancarlo Bisagni · Maria Sarobba · Antonio Russo · Ferdinando Riccardi · Lucia Del Mastro · Antonio Pazzola · Francesco Cognetti · Jennifer Foglietta · Stefania Gori · Francesco Nuzzo · Adriano Gravina · Michelino De Laurentiis · Roberto Bianco · Grazia Arpino · Sabino De Placido · Ciro Gallo · Francesco Perrone